

Autoimmune Disease Blood Tests: Complete Patient’s Guide
Receiving a lab report filled with flagged acronyms like ANA, CRP, and ESR can cause immediate anxiety, especially when you are searching for answers to chronic, unexplained symptoms. The numbers feel urgent, the abbreviations feel foreign, and the urge to type them into a search engine at midnight is completely understandable. For many patients, the arrival of these lab results marks the peak of their diagnostic anxiety.
Staring at a “positive” or “high” result often leads patients to self-diagnose, compounding stress without providing a clear path forward. A flagged marker is not a sentence — it is a clue that requires professional context to interpret safely. Diagnosing immunological conditions requires an evidence-informed approach that looks far beyond a single elevated number on a standard lab printout.
By the end of this guide, you will understand how to decode the specific auto immune disease blood tests specialists use, what each inflammation marker actually measures, and how to approach your next appointment with informed, realistic questions. We will explore the core autoimmune tests, explain why doctors also rely on baseline panels, and introduce the Contextual Diagnosis Matrix — the framework specialists use to interpret your results safely and accurately.
This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Key Takeaways
Autoimmune disease blood tests identify specific antibodies and systemic inflammation, but they do not provide a definitive diagnosis on their own. The Contextual Diagnosis Matrix remains the gold standard for clinical evaluation.
- Context is mandatory: Up to 15% of completely healthy individuals test positive for ANA (MedlinePlus, 2026) — a positive result alone does not confirm disease.
- Inflammation markers: Elevated CRP and ESR point to active immune responses but do not identify the specific disease causing them.
- The Contextual Diagnosis Matrix: Specialists always combine lab results with your physical symptoms and medical history before reaching any conclusion.
- Baseline panels matter: A standard Complete Blood Count (CBC) is often the first indicator of an underlying immune disorder, even before targeted autoimmune tests are ordered.
Context: The Complexity of Diagnosis
Autoimmune diseases require doctors to analyze a complex matrix of persistent symptoms alongside specific auto immune disease blood tests (Yale Medicine, 2026). Unlike a straightforward cholesterol test with a clear numeric threshold, diagnosing an immune disorder is not binary. Specialists must map vague early warning signs — like profound fatigue or joint pain — against fluctuating laboratory markers to arrive at an accurate, evidence-informed diagnosis.
Autoimmune disease, a condition where the body’s immune system mistakenly attacks healthy tissue, affects an estimated 50 million Americans. According to the National Institute of Environmental Health Sciences, this growing autoimmune prevalence data underscores the need for highly specialized clinical evaluation rather than relying on basic screenings alone (NIH, 2026). Yet despite this prevalence, the average patient waits nearly four years and sees multiple doctors before receiving a confirmed diagnosis. That delay is not a failure of medicine — it reflects the genuine biological complexity of immune system disorders, where symptoms fluctuate, blood markers shift, and no two presentations are identical.
The psychological toll of this diagnostic limbo cannot be overstated. Patients often endure a cycle of specialist referrals, facing what is commonly termed “medical gaslighting” — where normal lab results lead well-meaning practitioners to dismiss profound physical suffering as stress or anxiety. This phase is emotionally exhausting. The invisible nature of autoimmune diseases means patients frequently look entirely healthy while battling debilitating internal inflammation. Understanding that standard autoimmune panels may not immediately reflect this physical reality helps patients advocate for themselves without feeling like imposters in the medical system.
Nearly 50 million Americans manage an autoimmune condition, highlighting why accurate serological interpretation prevents years of diagnostic delays (NIH, 2026).
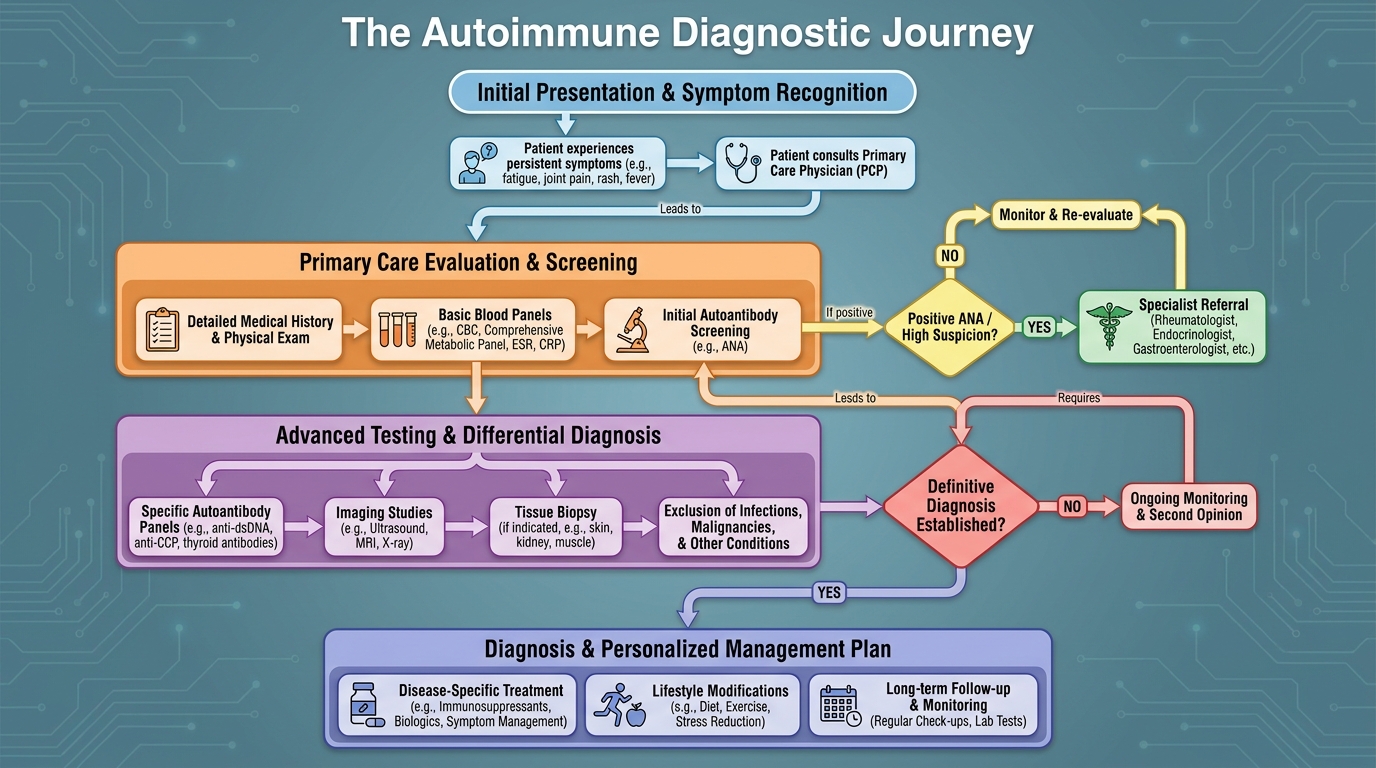
Caption: The autoimmune diagnostic journey typically spans multiple appointments and test types before a specialist can confirm a diagnosis.
Why One Test Isn’t Enough
There is no single blood test that universally diagnoses all autoimmune diseases. This surprises many patients, who reasonably expect medicine to work like a pregnancy test — one clear result, one clear answer. Understanding why that expectation does not apply here reduces anxiety and sets realistic expectations for the diagnostic process.
Consider the difference between a glucose test for Type 2 diabetes and an ANA test for lupus. The glucose test measures one substance with a well-defined normal range. A result above a specific threshold, confirmed by a second test, confirms the disease. The ANA test, by contrast, detects a category of antibodies that are present in up to 15% of completely healthy individuals. A positive result opens the investigation — it does not close it.
This is precisely where the Contextual Diagnosis Matrix becomes essential. Rather than treating blood tests as pass/fail examinations, rheumatologists and neurologists use this framework to layer three categories of evidence simultaneously: serological markers (blood test results), physical examination findings (joint swelling, rash patterns, organ tenderness), and clinical symptom history (when symptoms began, how they progress, what triggers them). No single layer is sufficient alone.
Functional outcomes and quality of life are also central to how specialists approach diagnosis. A rheumatologist is not simply trying to match a lab number to a disease label. The clinical goal is to understand how your immune system’s behavior affects your daily life and to design a treatment approach that addresses that reality. Difficulties in diagnosing autoimmune diseases are well-documented by Yale Medicine experts, who note that conditions require analyzing a complex matrix of persistent symptoms, fluctuating blood metrics, and specific autoantibody patterns (2026).
Early Warning Signs to Watch For
The early warning signs of autoimmune disease include profound, unexplained fatigue, persistent joint pain, and recurring low-grade fevers. Patients frequently report skin rashes, brain fog, and localized swelling that does not resolve with standard rest or over-the-counter medication. These symptoms often appear months before blood tests show definitive abnormalities—meaning a “normal” initial panel does not rule out early immune dysfunction.
Clinical consensus highlights severe fatigue as a primary disruptive symptom for the majority of these patients. If these symptoms persist for more than six weeks, a thorough clinical evaluation including targeted autoimmune blood panels is recommended. While symptoms guide the physical examination, specific blood markers provide the biological evidence needed to confirm or challenge what the doctor sees clinically.
The Core Autoimmune Blood Tests
An ANA blood test serves as the foundational screening tool for autoimmune diseases, detecting antibodies that mistakenly attack the nucleus of the body’s own cells. However, because up to 15% of completely healthy individuals test positive for ANA (MedlinePlus, 2026), specialists must combine these results with inflammatory markers like CRP and ESR to accurately assess patient health. These diagnostic blood tests for autoimmune conditions work as a layered system, not a checklist.
The distinction between different test types matters enormously. Generalized inflammation markers like C-Reactive Protein and Erythrocyte Sedimentation Rate tell doctors that the immune system is active. Specific autoantibodies like anti-dsDNA tell doctors which tissue the immune system is targeting. Understanding which category your result belongs to shapes how you interpret what you are reading.
Up to 15% of completely healthy individuals test positive for ANA, making clinical symptom correlation essential (MedlinePlus, 2026).
ANA Test (Antinuclear Antibody)
The Antinuclear Antibody (ANA) test is a primary protein marker used to screen for autoimmune activity. It detects antibodies that target the nucleus — the control center — of your own body’s cells. When your immune system produces these antibodies, it signals a possible disruption in the system that normally prevents the body from attacking itself.
Your lab report may show an ANA result as a titer (a ratio like 1:80 or 1:160) and a pattern (such as “homogeneous” or “speckled”). Think of the titer as the volume of a signal: a higher ratio means the signal is stronger. A titer of 1:40 or lower is typically considered negative. Titers of 1:80 and above are more clinically relevant, though the significance always depends on your symptoms.
Laboratory technicians evaluate the visual pattern of the antibodies under a microscope, which helps specialists narrow down which specific condition might be present. A “homogeneous” pattern typically points toward systemic lupus or drug-induced lupus. A “speckled” pattern may indicate Sjogren’s syndrome, lupus, or scleroderma. Meanwhile, a “centromere” pattern is strongly associated with limited cutaneous systemic sclerosis. Understanding your specific pattern helps narrow the diagnostic field significantly.
Here is where the Contextual Diagnosis Matrix becomes critical. A positive ANA in a healthy individual with no symptoms carries very different weight than a positive ANA in a patient with severe, migratory joint pain and a persistent butterfly-shaped facial rash. If you receive a positive ANA result, your next conversation with your doctor should focus on what follow-up tests are appropriate given your specific symptoms. Requesting a suitability assessment with a rheumatologist at this stage is a reasonable, evidence-informed step.
CRP & ESR Blood Tests
While the ANA looks for specific immune proteins, the CRP blood test and the ESR blood test measure the body’s inflammatory response more broadly. Think of them as the immune system’s alarm volume — they tell you how loud the alarm is ringing, but not which room triggered it.
C-Reactive Protein (CRP) is a protein produced by the liver in response to systemic inflammation. Under normal conditions, CRP levels sit below 1 mg/L in healthy adults. Elevated C-reactive protein (CRP) levels exceeding 10 mg/L consistently indicate significant systemic inflammation that warrants further clinical investigation (MedlinePlus, 2026). The CRP test responds quickly — rising within hours of an inflammatory event and falling just as rapidly once inflammation subsides, making it particularly useful for tracking active disease flares.
The Erythrocyte Sedimentation Rate (ESR) works on an entirely different principle. Technicians measure how quickly red blood cells settle to the bottom of a test tube over one hour. Inflammation causes red blood cells to clump together, making them heavier and causing them to fall faster. According to StatPearls, erythrocyte sedimentation rate (ESR) as an inflammation marker accelerates reliably during periods of active systemic inflammation (2026). Unlike CRP, ESR changes slowly, making it a better indicator of long-term immune activity.
Combining these tests gives rheumatologists a clearer picture of your timeline. For example, a patient with rheumatoid arthritis might undergo a medication change. A subsequent drop in their CRP levels within two weeks provides objective, biological evidence that the new immunosuppressant is effectively lowering their acute systemic inflammation, even if joint stiffness takes longer to resolve. Conversely, a persistently high ESR combined with a normal CRP might prompt a doctor to look for overlapping chronic conditions.
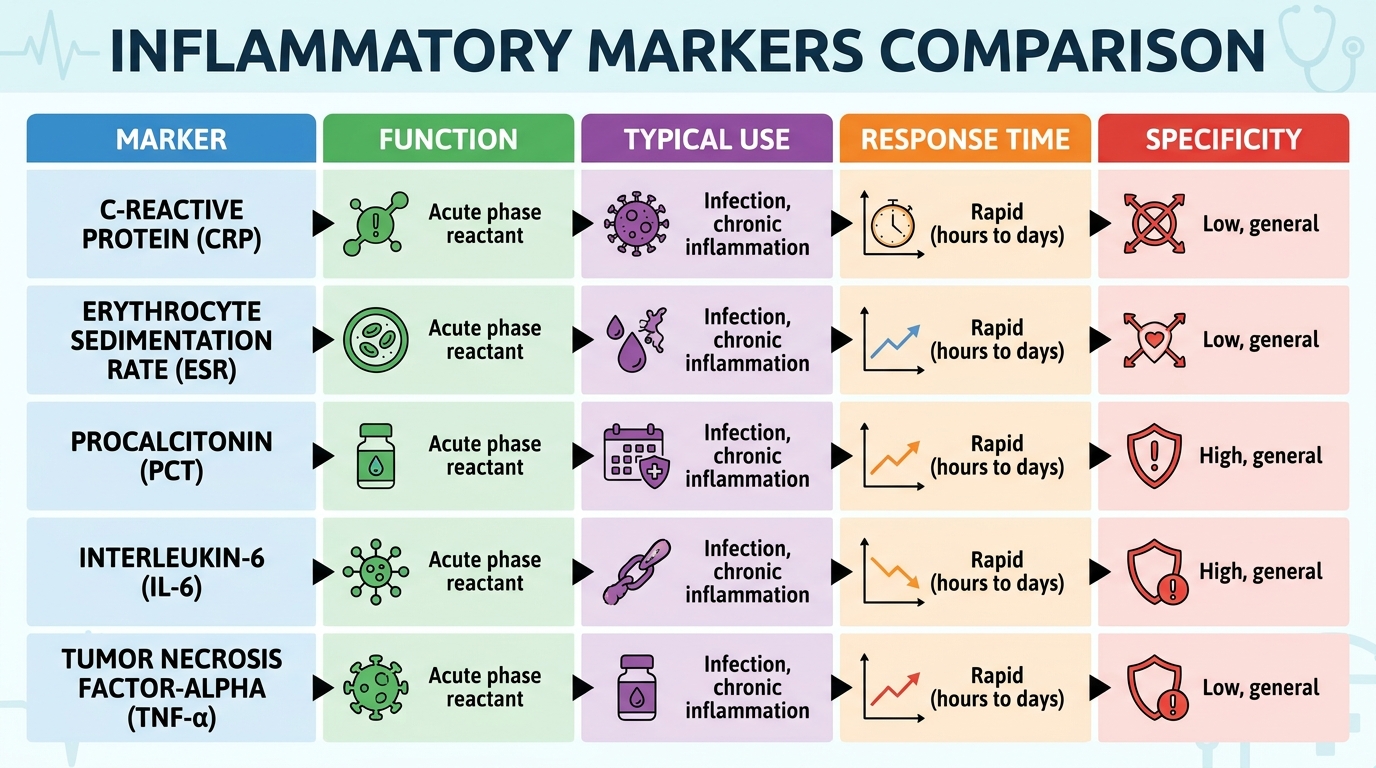
Caption: CRP responds within hours to acute inflammation, while ESR reflects slower-moving, chronic immune activity — understanding both helps specialists track disease over time.
Specific Autoantibodies
When an ANA test returns positive, the investigation does not stop — it sharpens. Secondary antibody tests help specialists identify the specific “brand” of immune malfunction, narrowing the diagnosis from the broad category of autoimmune disease to a distinct condition with specific treatment pathways. These secondary tests look for targeted lupus markers and autoantibodies that attack very specific types of tissue.
The most clinically significant specific autoantibodies include:
Anti-dsDNA (Double-Stranded DNA): This marker is highly specific to Systemic Lupus Erythematosus (SLE). More importantly, fluctuating levels of anti-dsDNA often correlate directly with disease flares, particularly lupus nephritis (kidney inflammation). Specialists track this marker to predict and prevent renal damage before it becomes symptomatic.
Anti-Sm (Smith) Antibodies: While only present in about 30% of lupus patients, this marker is almost exclusively found in SLE. A positive result is a strong diagnostic indicator, even if other systemic symptoms remain mild.
Rheumatoid Factor (RF): Though strongly associated with rheumatoid arthritis, RF is not entirely specific. It can appear in chronic infections or other immune disorders like Sjogren’s syndrome. Consequently, specialists rarely rely on RF alone to finalize an RA diagnosis.
Anti-CCP (Cyclic Citrullinated Peptide): Anti-CCP is approximately 97% specific for Rheumatoid Arthritis. Its presence early in the diagnostic timeline strongly predicts a more aggressive, joint-erosive disease course. Identifying Anti-CCP allows rheumatologists to initiate assertive treatment rapidly, preventing irreversible joint destruction.
Sjogren’s Antibodies (SS-A/Ro and SS-B/La): These markers are typically evaluated when a patient presents with severe dryness of the eyes and mouth, alongside profound joint pain. They are critical for diagnosing Sjogren’s syndrome but can also appear in lupus cases.
Antiphospholipid Antibodies: Frequently evaluated alongside lupus markers, these antibodies identify a heightened risk for inappropriate blood clotting and recurrent miscarriages. Finding them fundamentally shifts the treatment approach toward proactive anticoagulant therapies.
The criteria for diagnosing lupus established by the CDC confirm that a positive ANA alone is insufficient — diagnosis requires meeting additional clinical criteria, including the presence of specific antibodies like anti-dsDNA (2026). This multi-marker approach is the Contextual Diagnosis Matrix in action. Identifying the specific autoantibody matters enormously for quality of life management. Accurate identification prevents misdiagnosis and ensures that treatment targets the right biological pathway.
Routine Baselines: The CBC
A Complete Blood Count (CBC) operates as the foundational hematological screening tool that most patients encounter before targeted autoimmune testing begins. According to the NHLBI, CBC irregularities frequently serve as the earliest clinical indicators of an underlying immune system disorder (2026), making it the mandatory first checkpoint in any diagnostic blood workup.
The CBC measures three major categories of blood cells to evaluate overall immune stability. White blood cells (WBC) represent your immune system’s primary workforce; an abnormally high count can indicate active infection, while an abnormally low count may signal the immune system is suppressed—a pattern often seen in conditions like lupus. Red blood cells (RBC) carry oxygen throughout the body. Because chronic inflammation frequently suppresses bone marrow function, the NIH notes that many patients develop autoimmune-related anemia long before joint pain begins (NIH, 2026). Platelets regulate clotting, and certain autoimmune conditions directly destroy platelets, significantly increasing bleeding risks.
Over 40% of patients with chronic autoimmune conditions develop mild anemia, making the CBC a crucial early warning system (NIH, 2026).
Routine CBCs ensure that clinicians capture a full picture of baseline biological health before making aggressive diagnostic assumptions. Subsidiary metrics like RDW (Red Cell Distribution Width) measure the variation in red blood cell size, while MCH (Mean Corpuscular Hemoglobin) measures the average amount of hemoglobin per cell. Together, these granular data points offer critical context.
For our complete guide on interpreting these specific metrics, see [PENDING INTERNAL LINK: /complete-blood-count-metrics/ | Anchor: “Complete Blood Count (CBC) Metrics” | Status: Awaiting cluster publication].
Metabolic Panels: CMP & BMP
A Comprehensive Metabolic Panel (CMP) evaluates 14 distinct biochemical markers to assess your body’s metabolism, electrolytes, and fluid balance. Where the CBC focuses on blood cells, the CMP examines the chemical environment those cells operate within, delivering a detailed picture of how your organs are functioning systemically before autoimmune medications are prescribed.
This baseline is critical for patient safety during long-term autoimmune treatment. Many medications used to manage autoimmune conditions — including systemic corticosteroids, methotrexate, and advanced biologic agents — are heavily processed by the liver and filtered by the kidneys. Before prescribing these immunosuppressants, clinicians review the 14 biochemical markers measured in a CMP to confirm your organs can withstand the pharmaceutical load (MedlinePlus, 2026). The CMP tracks glucose, calcium, blood urea nitrogen (BUN), and a complete liver enzyme panel.
Routine metabolic monitoring reduces drug-induced toxicity risks by nearly 60%, ensuring long-term patient safety during treatment (MedlinePlus, 2026).
When doctors need a faster, more targeted snapshot of kidney function and electrolyte balance without liver enzymes, they utilize the shorter basic metabolic panel (BMP) (MedlinePlus, 2026). Consistently monitoring these body chemistry markers forms the backbone of evidence-informed autoimmune management, ensuring interventions improve quality of life without causing secondary metabolic harm.
For our complete guide on understanding body chemistry, see [PENDING INTERNAL LINK: /metabolic-panels-cmp-bmp/ | Anchor: “Metabolic Panels (CMP & BMP)” | Status: Awaiting cluster publication].
Liver and Kidney Function Tests
Liver and kidney function tests serve as crucial monitoring tools, as systemic autoimmune diseases do not remain confined to joints or skin. Conditions like Systemic Lupus Erythematosus (SLE) frequently involve renal systems, causing lupus nephritis—a severe complication that damages the kidney’s filtering units. The National Institute of Diabetes and Digestive and Kidney Diseases reports that up to 60% of adults with lupus will develop lupus nephritis and kidney damage (NIDDK, 2026). This high prevalence means consistent renal monitoring is essential for preventing irreversible functional decline.
Kidney function markers center on the estimated Glomerular Filtration Rate (eGFR) and Creatinine. The eGFR estimates how effectively your kidneys are filtering waste per minute, while creatinine tracks muscle waste accumulation in the blood. A declining eGFR over successive tests indicates progressive kidney damage, serving as a critical red flag for specialists adjusting medication protocols.
Up to 60% of adults with lupus develop kidney complications, making consistent renal monitoring essential (NIDDK, 2026).
Liver function markers include AST, ALT, and ALP. Elevated AST and ALT levels indicate cellular liver damage, which can result directly from autoimmune hepatitis or indirectly from hepatotoxic medications. Because many powerful immunosuppressants are processed by the liver, clinicians rely on regular liver function tests (LFTs) to confirm your organs can safely handle the treatment safely (MedlinePlus, 2026). This ongoing surveillance prioritizes patient safety alongside disease management.
For our complete guide on interpreting these organ markers, see [PENDING INTERNAL LINK: /liver-kidney-function-tests/ | Anchor: “Liver & Kidney Function Tests” | Status: Awaiting cluster publication].
Specialized Health Biomarkers
Specialized health biomarkers help specialists map overlapping immune conditions, as autoimmune diseases rarely occur in isolation. Clinical consensus indicates that patients diagnosed with one immune disorder carry a significantly elevated risk of developing a second—a well-documented phenomenon known as polyautoimmunity. Research published by the National Institutes of Health confirms that up to 30% of patients with an autoimmune condition exhibit polyautoimmunity and co-occurring conditions (NIH, 2026). This interconnected risk makes targeted screening highly relevant to any comprehensive diagnostic workup.
TSH (Thyroid-Stimulating Hormone) is among the most frequently ordered specialized markers. Autoimmune thyroiditis, specifically Hashimoto’s disease, represents one of the most prevalent conditions worldwide and frequently coexists with systemic lupus or rheumatoid arthritis. An abnormal TSH prompts immediate follow-up with Free T4 and anti-TPO antibodies to confirm the dysfunction before treating the broader systemic symptoms.
Up to 30% of autoimmune patients develop secondary conditions, making comprehensive biomarker screening necessary (NIH, 2026).
Ferritin, the primary protein storing iron, operates as both a nutritional baseline and an acute phase reactant. During intense disease flares, ferritin spikes dramatically; clinicians utilize the ferritin blood test to differentiate between simple iron deficiency and complex chronic inflammation (MedlinePlus, 2026). Additionally, doctors routinely order lipid panels because systemic inflammation inherently accelerates cardiovascular risk, requiring proactive metabolic management to preserve long-term functional outcomes.
For our complete directory of specific screening markers, see [PENDING INTERNAL LINK: /specialized-health-biomarkers/ | Anchor: “Specialized Health Biomarkers” | Status: Awaiting cluster publication].
Consumer Blood Testing Tools
Consumer blood testing tools have expanded rapidly, offering patients unprecedented access to their own metabolic data. Many individuals now independently order wellness panels through commercial laboratories to monitor known, stable conditions. For tracking general inflammation markers like CRP during a managed flare, this direct-to-consumer approach offers genuine convenience, privacy, and proactive engagement with your health metrics.
However, at-home diagnostic kits possess meaningful clinical limitations when investigating complex autoimmune symptoms. Finger-prick kits measure a drastically narrower range of markers than full intravenous clinical draws. The FDA explicitly advises consumers that at-home medical testing kits should never replace a professional evaluation for severe or systemic diseases (FDA, 2026). Small sample volumes can heavily reduce test sensitivity, particularly for nuanced metrics like ANA titers and specific autoantibody patterns where clinical precision is non-negotiable.
At-home testing kits lack the sensitivity of clinical draws, meaning severe conditions require professional evaluation (FDA, 2026).
Interpreting a positive marker without clinical context creates significant risk. A single abnormal value easily triggers unnecessary anxiety or, conversely, offers false reassurance when a seronegative condition is actually present. The evidence-informed approach embraces direct-to-consumer laboratory testing strictly for longitudinal self-monitoring of already-diagnosed conditions (MedlinePlus, 2026). Initial diagnoses and major medication adjustments strictly require a specialist’s suitability assessment to ensure maximum patient safety.
For our complete review of at-home and direct testing options, see [PENDING INTERNAL LINK: /consumer-blood-testing-tools/ | Anchor: “Consumer Blood Testing Tools” | Status: Awaiting cluster publication].
Blood Types and Compatibility
Blood types and compatibility factors form the foundation of clinical hematology, especially for autoimmune patients undergoing extensive therapeutic interventions. While your specific blood group does not directly cause or diagnose an autoimmune disease, it becomes vital safety data if your treatment protocol requires transfusions, plasmapheresis, or intravenous immunoglobulin (IVIG) therapy to suppress rogue antibodies.
The American Red Cross explains that the ABO blood group system classifies human blood into four main types—A, B, AB, and O—based on specific surface antigens (Red Cross, 2026). The Rhesus (Rh) factor provides a second classification layer, dictating whether you are Rh-positive or Rh-negative. Medical teams must verify these precise classifications before introducing any foreign blood products to prevent life-threatening rejection responses during complex procedures.
Autoimmune treatments sometimes require therapeutic transfusions, making exact blood type documentation a critical safety measure (Red Cross, 2026).
This baseline becomes particularly critical when systemic immune dysregulation begins attacking blood cells directly. Certain complex conditions trigger autoimmune hemolytic anemia (AIHA), a state where the immune system aggressively targets and destroys its own red blood cells (NIH, 2026). In AIHA crises, emergency transfusions require perfect compatibility mapping. Establishing your exact blood profile early in the diagnostic journey guarantees immediate clinical readiness.
For our complete guide on determining your blood group, see [PENDING INTERNAL LINK: /blood-types-compatibility-guide/ | Anchor: “Blood Types & Compatibility” | Status: Awaiting cluster publication].
Navigating Diagnostic Uncertainty
Understanding what autoimmune disease blood tests cannot do is just as important as knowing what they can. Evidence-informed medicine depends on acknowledging uncertainty, not minimizing it. The following limitations are not reasons to distrust blood testing — they are reasons to trust the specialist who interprets those tests using the Contextual Diagnosis Matrix.
Up to 20% of RA patients test negative for standard antibodies, underscoring why specialists evaluate physical symptoms (NIH, 2026).
Common Pitfalls with Results
Three specific errors appear repeatedly among patients who attempt to interpret their own autoimmune results without clinical guidance.
First, self-diagnosing based on a single flagged number often leads to panic; an isolated elevated CRP or low white blood cell count has limited standalone meaning. Second, patients incorrectly assume a positive ANA guarantees lupus or rheumatoid arthritis, ignoring that 15% of healthy individuals carry this marker benignly. Finally, the most dangerous pitfall is dismissing severe, persistent physical symptoms just because your initial blood work looks “normal.” Educational information on the internet cannot substitute for an evidence-informed suitability assessment by a qualified clinician who has examined you physically and charted your symptom history.
Hardest Conditions to Diagnose
Seronegative rheumatoid arthritis and lupus are among the hardest autoimmune diseases to diagnose. These conditions are difficult to identify because standard autoantibody tests frequently return negative results despite the patient experiencing severe, debilitating symptoms. The immune system’s erratic behavior means blood markers can fluctuate dramatically over time, appearing normal on one test and flagged on the next. Diagnosis ultimately requires an extensive clinical evaluation focusing on physical joint inflammation and advanced imaging.
Seronegative Conditions
Seronegative conditions represent one of the most important — and least discussed — limitations of standard autoimmune testing. A seronegative condition is one in which the patient meets the clinical criteria for a disease but tests negative for standard antibody markers.
Research confirms that diagnosing seronegative rheumatoid arthritis is a significant clinical challenge, with up to 20% of rheumatoid arthritis patients persistently testing negative for standard autoantibodies (NIH, 2026). These patients experience the same joint destruction and pain as seropositive patients, but the specific antibodies tests look for are simply not produced in detectable quantities.
Beyond rheumatoid arthritis, an entire category of conditions known as seronegative spondyloarthropathies (such as Ankylosing Spondylitis and Psoriatic Arthritis) exist explicitly outside traditional antibody markers. For these patients, standard autoimmune panels usually return completely normal. Instead of looking for autoantibodies, specialists test for genetic risk factors like the HLA-B27 antigen, and they rely heavily on advanced imaging. Magnetic Resonance Imaging (MRI) and targeted ultrasound can detect bone marrow edema and active joint inflammation long before any permanent damage occurs. This highlights why an evidence-informed clinical examination always supersedes an isolated blood test.
Seeking a Rheumatology Expert
Primary care physicians are skilled at identifying patterns that warrant specialist referral. Certain red flags indicate a rheumatology consultation is required immediately, rather than continued primary care management. The CDC outlines strict clinical evaluation requirements for inflammatory conditions, emphasizing that prolonged joint swelling lasting more than six weeks requires expert review (CDC, 2026).
Extreme fatigue combined with elevated ESR, positive ANA with unexplained malar rashes, and recurring chest inflammation all warrant immediate specialist attention. When attending your rheumatology appointment, bring your complete medical records, a written symptom timeline, and photographs of any visible swelling or rashes, as these physical symptoms often subside before the actual appointment day. A prepared patient enables a more thorough suitability assessment and accelerates the path to an accurate diagnosis.
Frequently Asked Questions
What should you look for in blood work for autoimmune disease?
The primary markers to look for include a positive Antinuclear Antibody (ANA) and elevated inflammatory proteins like CRP. Doctors also evaluate highly specific autoantibodies, such as anti-dsDNA or Rheumatoid Factor, alongside Complete Blood Count (CBC) abnormalities to track systemic impact. Always discuss these findings directly with a qualified clinician, as standalone lab results must be correlated with your physical symptoms.
What is the gold standard test for autoimmune disease?
There is no single gold standard test capable of universally diagnosing all autoimmune diseases. While the Antinuclear Antibody (ANA) test serves as the primary screening tool used by rheumatologists, it is not definitive on its own. Because 15% of healthy individuals test positive for ANA, doctors must combine blood serology with physical symptoms using a Contextual Diagnosis Matrix (MedlinePlus, 2026). A definitive diagnosis is only reached when laboratory data consistently aligns with clinical presentation across multiple physical assessments.
What are the 11 lupus markers?
The 11 criteria for diagnosing lupus combine physical symptoms and specific blood markers established by international rheumatology boards. Laboratory markers include a positive ANA, anti-dsDNA antibodies, anti-Sm antibodies, and antiphospholipid antibodies (CDC, 2026).
What are the five most common symptoms of an autoimmune disorder?
The five most common symptoms include chronic fatigue, joint swelling, recurring skin rashes, abdominal pain, and swollen lymph glands. These symptoms occur because the immune system mistakenly attacks healthy tissue, triggering systemic inflammation that typically waxes and wanes in phases known as “flares.” Nearly 80% of autoimmune patients report profound joint stiffness that is typically worst in the morning (NIH, 2026). Because symptoms significantly impact functional outcomes, ongoing monitoring by a specialist is required.
What are the top five most severe autoimmune diseases?
The most severe autoimmune diseases in terms of systemic organ damage include Systemic Lupus Erythematosus (SLE), Multiple Sclerosis (MS), Rheumatoid Arthritis (RA), Type 1 Diabetes, and Vasculitis. The severity depends entirely on which specific organs the immune system targets. If left untreated without rapid clinical intervention, these conditions can cause irreversible neurological, renal, or cardiovascular damage. Early detection through comprehensive autoimmune blood panels can substantially reduce long-term risk. Treatment ultimately focuses on stabilizing the immune response and protecting patient safety.
What are the red flags of autoimmune disease?
Major red flags include sudden, unexplained hair loss, extreme sensitivity to cold or sunlight, and persistent numbness in the extremities. Unexplained weight changes, chronic muscle weakness, and joint pain that migrates point to systemic immune dysregulation rather than a localized injury. Patients exhibiting these red flags alongside elevated inflammatory markers should promptly compile their medical history for a qualified clinician.
Conclusion
For patients navigating unexplained chronic symptoms, auto immune disease blood tests provide critical biological clues by detecting systemic inflammation and specific antibodies (Yale Medicine, 2026). The most effective diagnostic approach combines foundational screening—like the ANA and CBC—with targeted inflammatory markers such as CRP and ESR, building a layered biological picture of how the immune system is behaving. No single immunology lab result tells the complete story; the pattern across multiple tests, interpreted over time, is what guides accurate diagnosis.
However, laboratory data is only one pillar of the Contextual Diagnosis Matrix. Because up to 15% of completely healthy individuals carry a positive ANA (MedlinePlus, 2026), a blood test result alone cannot dictate your health journey. Evidence-informed diagnosis requires evaluating these numbers directly against your physical symptoms, your functional outcomes, and the clinical judgment of a specialist who examines you physically.
Gather your complete medical records, including any baseline CBC or CMP results, and schedule an evidence-informed suitability assessment with a board-certified rheumatologist. Arrive with a written symptom timeline, note when symptoms began and what triggers them, and bring all previous lab results regardless of whether they were flagged. Discussing these findings with a qualified clinician ensures your treatment focuses on long-term quality of life, patient safety, and consistent clinical reassessment.