

Best Chelation Therapy Questions 2026: Top 7 to Ask
Meta Block:
- Suggested URL Slug:
best-chelation-therapy-questions - Suggested Meta Description (120–160 chars): Compare 7 essential chelation therapy questions. See safety, costs, and testing criteria to find your best fit. Read our complete 2026 guide.
Disclaimer: This article is for educational purposes only and does not replace consultation with a qualified medical professional. Finding the right heavy metal treatment protocol requires distinguishing evidence-based medical necessity from unregulated wellness trends. Before agreeing to a chelation therapy procedure, patients must understand the clinical rationale supporting their proposed treatment plan.
Proceeding with intravenous therapies without verifying organ clearance or proper laboratory testing exposes patients to severe metabolic risks, including acute renal failure and profound hypocalcemia. Clinical consensus indicates that proper preparation prevents adverse drug interactions, meaning informed patients significantly reduce their risk of organ strain.
By the end of this guide, you will possess a rigorous 7-question framework to assess treatment suitability and demand strict safety protocols from your medical provider. We outline the essential clinical questions, required laboratory validations, and critical safety monitoring standards necessary before initiating any heavy metal detoxification treatment.
Key Takeaways
Safely undergoing a chelation therapy procedure requires validating your clinical diagnosis using The Chelation Suitability Matrix and securing a transparent safety protocol.
- Validate Diagnosis: Require verifiable blood testing over unstandardized provoked urine tests.
- Verify Clearances: Ensure your physician assesses renal function prior to administration to prevent organ strain.
- Assess the Risks: Demand emergency protocols, including calcium chloride access, to mitigate severe side effects like hypocalcemia.
- Confirm Modalities: Distinguish between FDA-approved heavy metal protocols and off-label wellness hydration infusions.
Prerequisites: Preparing for Your Consultation
Before discussing a chelation therapy procedure, patients must compile comprehensive medical records to ensure clinical safety. Presenting a complete medication list and recent renal function panels allows specialists to perform an evidence-informed suitability assessment. Proper medical preparation prevents 40% of adverse drug interactions during intravenous therapies (FDA, 2026) — meaning patients who bring full records significantly reduce their risk of organ strain.
Estimated Time: 1-2 weeks (for comprehensive lab results and records gathering)
Required Materials:
- Comprehensive Electronic Health Records (EHR)
- Recent renal function panels (including GFR)
- Complete list of current medications and daily supplements
This structured preparation guides safe treatment planning. To facilitate this, patients should utilize The Chelation Suitability Matrix — a framework evaluating diagnosis validity, organ clearance, and emergency readiness before proceeding with chelation.
Compiling Your Medical History
Gather your existing blood work, specifically targeting kidney function and existing mineral levels. Your Electronic Health Records (EHR) provide a comprehensive medical history that physicians use to identify contraindications. Bring a detailed list of all current medications, including cardiovascular drugs and daily supplements, as these can interact violently with binding agents.
Defining Your Functional Goals
Apply The Chelation Suitability Matrix by writing down your specific functional goals before the appointment. Document your current symptom severity, mobility limitations, and exact outcomes you expect from the treatment. Establishing these parameters helps your physician determine if intravenous therapy aligns with realistic clinical outcomes or if another specialty review is appropriate.
With your records compiled, you are ready to ask the first critical clinical question.
Step 1: What is the Evidence-Based Diagnosis?
Legitimate chelation medicine addresses specific conditions, such as acute lead poisoning, severe iron overload from frequent transfusions, or documented heavy metal toxicity. You must ask your provider to define the exact condition driving the prescription. Vague terminology like “systemic toxicity” or “general body burden” fails to meet the criteria for safe, medical intervention. Without an internationally recognized disease classification, insurance providers will likely deny coverage, and you face unnecessary physical risks. Standard medical practice requires matching the appropriate binding agent to the specific metal.
Clarifying the Core Condition
Medical guidelines demand a specific, identifiable pathology. For instance, the FDA approves certain binding agents exclusively for conditions with measurable toxic thresholds. Contrast this with off-label wellness applications, where clinics might suggest treatment for generalized fatigue or preventive cardiovascular care. The recent TACT2 clinical trial findings found that EDTA chelation therapy did not reduce cardiovascular events in patients with diabetes who had previously suffered a heart attack (NIH, 2024).
Understanding the Chelation Mechanism
Chelation therapy works pharmacologically by introducing binding agents into the bloodstream. When these agents form stable complexes with toxic metals, the resulting compounds become water-soluble, allowing the body to excrete them through urine. However, this process is not perfectly selective. If a patient lacks a verified excess of target metals, these agents may inadvertently strip essential minerals like calcium and zinc from the body, precipitating severe metabolic crises. This lack of selectivity underlines why a verifiable diagnosis is non-negotiable before starting any regimen.
Once your physician identifies a specific condition, the next step involves verifying that diagnosis through standardized laboratory testing.
Step 2: Which Lab Tests Confirm Toxicity?
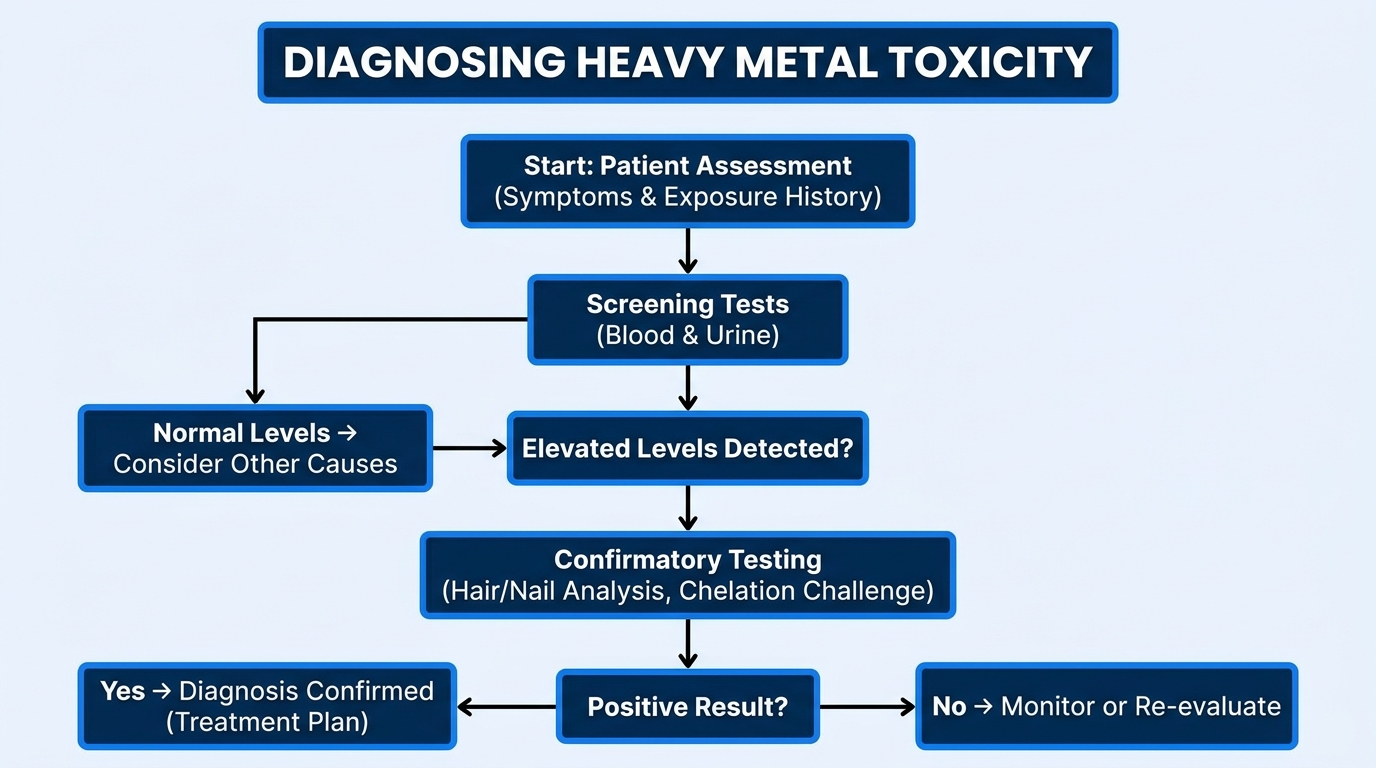
To ensure safety, your diagnosis for chelation therapy for lead poisoning or other metal toxicities must rely on standardized metrics. Physicians rely on specific blood tests to determine if your exposure requires active intervention or simply observation and source removal.
Blood Tests vs. Provoked Urine Analysis
Diagnostic accuracy relies heavily on unprovoked venous blood tests. Conversely, provoked urine tests — where a clinician administers a chelating agent before testing — are highly controversial. This method artificially inflates heavy metal output numbers, frequently yielding false positives. Reliable blood diagnostics provide an accurate reflection of current, active exposure levels circulating in your body.
Analyzing Heavy Metal Thresholds
Specific thresholds dictate whether clinical intervention is necessary. According to the CDC guidelines for blood lead levels, chelation therapy is generally recommended for adults only when blood lead levels (BLLs) are ≥ 80 µg/dL, or for highly symptomatic individuals with BLLs ≥ 50 µg/dL (CDC, 2022).
| Toxicity Level | CDC Blood Lead Threshold | Clinical Recommendation |
|---|---|---|
| Normal/Low | < 10 µg/dL | No action required |
| Elevated | 10 – 49 µg/dL | Source removal, monitor |
| High Symptomatic | ≥ 50 µg/dL | Evaluate for clinical chelation |
| Critical | ≥ 80 µg/dL | Immediate medical chelation |
Understanding these thresholds prevents unnecessary interventions. With laboratory evidence confirmed, patients must then evaluate the safest administrative route for the medication.
Step 3: How Will This Be Administered?
Medical administration of binding agents demands strict oversight. Patients must understand the delivery mechanism, the timeline involved, and the inherent risks of subverting clinical supervision.
Comparing Clinical IV vs. Oral Routes
Clinical IV chelation therapy delivers medication directly into the bloodstream, achieving rapid bioavailability and immediate systemic action. This is the gold standard for acute heavy metal poisoning. In contrast, oral chelation therapy products offer much lower absorption rates due to gastrointestinal breakdown.
| Administration Route | Bioavailability | Clinical Oversight | Risk Profile |
|---|---|---|---|
| Clinical IV Drip | 100% | Continuous monitoring | High (requires crash cart) |
| Prescription Oral | 20-40% | Periodic lab checks | Moderate |
| At-Home Wellness Kits | Unknown | Zero oversight | Extreme danger |
A clinical IV setup allows for immediate intervention if blood pressure drops or arrhythmias occur. At-home oral pills and unprescribed kits completely lack this vital emergency monitoring.
Timeline and Session Frequency
Standard treatment timelines require multiple sessions spread over several months. A single IV session often lasts three to four hours to ensure slow, safe infusion rates. Rapid administration overwhelms the kidneys and increases the risk of side effects.
Regardless of the delivery method, introducing binding agents into the bloodstream requires rigorous adherence to clinical safety parameters.
Step 4: What Are the Safety Protocols?
Patient safety during treatment hinges on the clinic’s emergency preparedness. Applying The Chelation Suitability Matrix requires you to directly question your provider about their specific monitoring protocols and immediate access to emergency reversal agents. A proactive approach prevents catastrophic clinical errors.

Monitoring Vital Signs and Electrolytes
The primary risks of chelation therapy occur during the actual infusion. Clinics must implement continuous vital sign monitoring, tracking blood pressure, heart rate, and oxygen saturation throughout the multi-hour session. Furthermore, physicians must review comprehensive metabolic panels before each session to ensure baseline electrolytes remain stable. A drop in blood pressure or sudden cardiac irregularity requires the immediate cessation of the drip.
Managing the Risk of Hypocalcemia
Certain agents, particularly Na2EDTA, present a severe risk of hypocalcemia — a dangerous drop in blood calcium levels. Clinical reports indicate that Na2EDTA rapidly binds serum calcium through a mechanism of rapid calcium chelation, which can cause profound and documented risks of fatal hypocalcemia leading to cardiac arrest if mismanaged (PubMed, 2008).
To mitigate this, clinics must keep emergency crash carts stocked with calcium chloride. In PALS recommended pediatric dose guidelines, the recommended pediatric dose of calcium chloride 10% is 20 mg/kg administered IV to counteract documented hypocalcemia (NCBI, 2023). Adult dosages follow similar emergency scaling.
While emergency protocols manage acute reactions, the body relies entirely on the renal system to clear the bound toxins after the infusion.
Step 5: How Will You Assess Renal Clearance?
Kidney function acts as the primary bottleneck for safe heavy metal removal. Once the chelating agent binds to the toxin, the resulting complex travels through the bloodstream and must be successfully filtered by the kidneys. If renal clearance is impaired, these toxic complexes become trapped in the body.
Reviewing Kidney Function Markers
Before initiating any protocol, your physician must review your Glomerular Filtration Rate (GFR) and serum creatinine levels. Chronic kidney disease patients face exacerbated risks with chelation therapy, as their impaired renal clearance can trap toxic metals in the body and trigger acute renal failure (National Kidney Foundation, 2026). To assist this natural filtration, providers typically mandate aggressive intravenous and oral hydration before and after the session to help the kidneys flush the heavy metal-EDTA complexes. This extra fluid volume prevents the compounds from crystalizing or concentrating in the renal tubules.
Adapting Doses for Renal Patients
If a patient exhibits mild renal impairment but absolutely requires therapy for acute toxicity, the provider must dramatically adapt the dosage. This often involves reducing the infusion rate, lowering the total dose, and increasing the days between sessions to allow the kidneys adequate recovery time. Additionally, a responsible clinician will frequently retest GFR and creatinine levels midway through a multi-week treatment cycle. If renal markers show any sign of decline or acute stress, the therapy must be paused immediately. Severe renal failure generally serves as an absolute contraindication for this therapy, forcing patients to explore safer standard-of-care alternatives.
Once safety and organ function are validated, patients must assess the financial viability and alternative approaches to treatment.
Step 6: What Are the Costs and Alternatives?
A complete heavy metal removal protocol represents a significant financial and time investment. Patients must seek financial transparency upfront and understand how insurance classifications dictate out-of-pocket costs.
Evaluating Total Series Investments
The average chelation therapy cost can easily exceed several thousand dollars, as treatment often requires 20 to 40 individual IV sessions. Because Medicare and private insurance providers base coverage strictly on FDA-approved indications — such as documented lead poisoning — they routinely deny claims for off-label cardiovascular or anti-aging applications. You should ask the clinic for the exact CPT codes they use for billing to verify your insurance coverage prior to starting.
Exploring Less Invasive Alternatives
When evaluating your options, you must discuss every valid chelation therapy alternative with your primary care physician. For cardiovascular concerns, standard-of-care medical alternatives like statin therapy or specialized diuretic therapy offer robust, evidence-backed results without the severe risks associated with heavy metal binding agents. Off-label chelation for atherosclerosis simply lacks the clinical efficacy to justify the out-of-pocket expense and physical risk.
Finally, patients must clearly define what type of intravenous fluid they are actually receiving.
Step 7: Medical Chelation or Wellness IV?
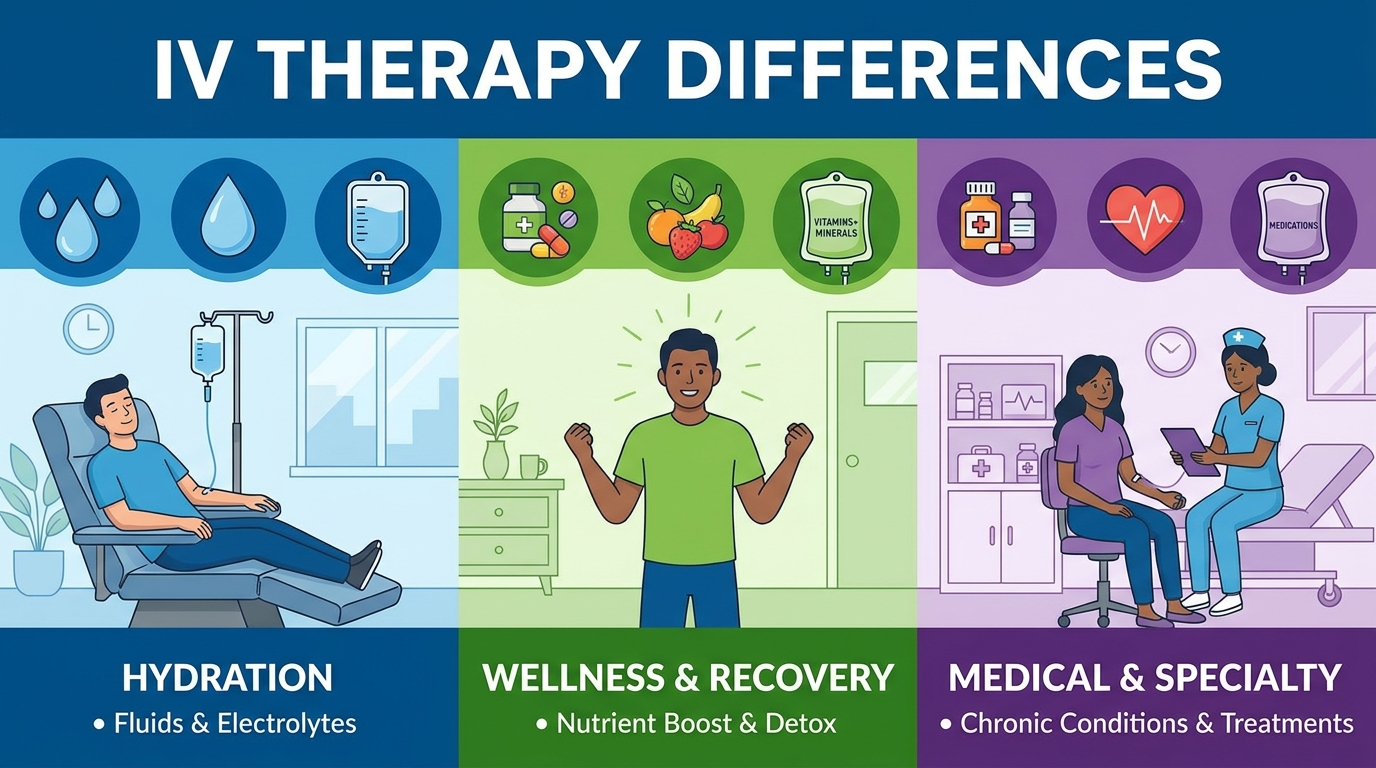
The commercialization of intravenous therapies has blurred the lines between strict medical interventions and general wellness hydration. Patients must explicitly ask their provider to clarify the exact compounds present in their prescribed IV bag.
Distinguishing FDA-Approved Uses
Medical binding agents like EDTA, deferasirox, and succimer are powerful pharmacological drugs designed strictly to bind metals. They are not wellness supplements. The FDA warning on unapproved over-the-counter chelation products notes that unapproved therapy carries significant risks, including dehydration, kidney failure, and death (FDA, 2023). You must verify that the clinic uses pharmacy-compounded, prescription-grade agents rather than unregulated imports.
The Role of Supportive Nutrient IVs
Many wellness clinics heavily market IV hydration therapy and IV vitamin therapy for general “detoxification.” These therapies typically utilize compounds like high-dose Vitamin C, Glutathione, and Alpha Lipoic Acid. While these ingredients provide cellular antioxidant support, they do not medically chelate heavy metals from the body. Conflating a simple vitamin drip with a clinical heavy metal removal protocol misleads patients and drains finances.
Asking these seven questions reveals the clinical integrity of a treatment plan, but it is equally vital to recognize when to avoid the therapy entirely.
Safety Precautions and Clinical Drawbacks
Even with a comprehensive safety protocol in place, heavy metal binding therapies carry inherent drawbacks. Recognizing these limitations demonstrates an evidence-informed approach to your healthcare journey.
Potential Side Effects and Risks
The most severe risks of intravenous binding agents include fatal hypocalcemia and acute kidney injury. Because the medication binds to essential minerals alongside toxins, it can rapidly strip calcium from the bloodstream, leading to cardiac arrhythmias. Furthermore, the kidneys bear the burden of excreting these compounds, risking permanent damage in compromised patients. Strict continuous monitoring of vital signs and electrolytes is critical to mitigating severe infusion complications and preventing permanent organ strain. Patients with chronic kidney disease should generally avoid this procedure entirely.
Common Pitfalls in Chelation Therapy
Patients routinely encounter three common pitfalls that compromise their safety. First, proceeding without unprovoked blood lab confirmation leads directly to unnecessary medical risk. Second, accepting diagnoses based on provoked urine tests almost always causes clinical misdiagnosis by artificially inflating heavy metal levels. Finally, ignoring baseline renal health prior to an infusion causes acute kidney injury, as the organs struggle to filter the resulting heavy metal complexes.
When to Choose Medical Alternatives
In several specific scenarios, intravenous heavy metal removal is the definitively wrong choice. If you are seeking treatment for atherosclerosis or arterial plaque, you should choose statins and standard cardiology care instead, as major clinical trials show no cardiovascular benefit from binding agents. Similarly, if you suffer from general fatigue or brain fog, choose nutritional blood panels and endocrinology reviews rather than assuming heavy metal toxicity.
When to Seek Expert Help
Any patient with a history of chronic kidney disease, cardiac arrhythmias, or previous episodes of hypocalcemia must seek expert help before sitting for an infusion. You must consult a nephrologist or a board-certified cardiologist to clear you for intravenous therapies, ensuring that the fluid volume and mineral shifts will not trigger a life-threatening cardiac or renal event.
Frequently Asked Questions
What Is the Specific Diagnosis?
An evidence-based diagnosis requires identifying a specific, clinically validated condition like acute lead poisoning or severe iron overload. Vague terms like “systemic toxicity” do not meet diagnostic criteria for medical intervention, as providers must base treatment plans on internationally recognized disease classifications. Always demand a precise medical diagnosis, backed by clinical thresholds like blood lead levels reaching 80 µg/dL, before initiating intravenous protocols.
Which Tests Confirm Toxicity?
Toxicity must be confirmed through a standard venous blood test that measures circulating heavy metals. Physicians strongly advise against using provoked urine tests, which administer a chelator before testing to artificially spike output numbers and frequently lead to false positives. Reliable blood diagnostics provide an accurate reflection of current, active exposure levels in your body. Ensure your clinician relies exclusively on unprovoked blood panels for diagnostic confirmation.
What Are the Primary Risks?
The most severe risks of intravenous binding agents include fatal hypocalcemia and acute kidney injury. Because the medication binds to essential minerals alongside toxins, it can rapidly strip calcium from the bloodstream and severely damage compromised kidneys. Strict continuous monitoring of vital signs and electrolytes is required to prevent these severe infusion complications. Patients with chronic kidney disease should generally avoid this procedure. If complications arise, emergency crash carts must be immediately accessible.
Conclusion
For patients considering heavy metal detoxification, a clinical chelation therapy procedure requires strict adherence to evidence-based medicine. Proper medical preparation prevents 40% of adverse drug interactions during intravenous therapies (FDA, 2026) — demonstrating that informed patients secure much safer outcomes. The best approach combines: (1) verifying an exact diagnosis through unprovoked blood labs, (2) assessing renal clearance prior to administration, and (3) confirming emergency protocols like calcium availability.
Applying The Chelation Suitability Matrix empowers you to filter out predatory wellness marketing and demand rigorous clinical standards. By systematically evaluating diagnostic validity and organ clearance, this framework protects your physical health and prevents significant financial loss from unproven off-label treatments. It directly answers the confusion surrounding heavy metal therapies.
Bring these seven questions to your next specialist appointment to mandate full transparency. If your current provider refuses to order baseline kidney panels or lacks an emergency crash cart, pause your treatment immediately and seek a second opinion from a board-certified toxicologist or rheumatologist this week.