

Autoimmune Medical Records to Bring: Complete Guide
MEDICAL DISCLAIMER: This article is for educational purposes only and does not replace consultation with a qualified medical professional. Always discuss your symptoms, testing, and treatment suitability with a board-certified clinician.
Navigating the healthcare system with unexplained joint inflammation is exhausting, particularly when critical medical history gets lost between different hospital networks. You may have seen three separate physicians, undergone multiple blood draws, and still arrived at a specialist’s office to find your records either incomplete or entirely absent.
Relying on electronic health records (EHR) to automatically transfer your clinical data often results in missing baseline information, forcing specialists to order duplicate tests and delaying crucial diagnostic answers. This fragmentation is not a reflection of your care team’s competence — it is a structural problem built into how separate hospital systems communicate across disparate software platforms.
By the end of this guide, you will know exactly how to compile the Medical Records To Bring For Autoimmune Or Joint Inflammation Symptoms so you can secure an accurate suitability assessment faster. We will walk through five foundational steps — from collecting unsummarized blood work and raw imaging files to organizing clinical notes and personal symptom logs into a single, comprehensive binder.
In our experience analyzing clinical intake protocols across major hospital networks, patients who assume passive roles often face delayed treatments. Conversely, those who arrive with fully consolidated evidence shift the consultation dynamic immediately.
Key Takeaways
The most critical Medical Records To Bring For Autoimmune Or Joint Inflammation Symptoms include unsummarized blood work, raw DICOM imaging files, and detailed symptom logs.
- Build a physical binder: Prevents delays caused by hospital interoperability gaps.
- Demand unsummarized labs: Provide 12–24 months of raw numeric data.
- Secure DICOM files: Specialists require raw imaging on CDs or flash drives.
- Utilize The 360-Degree Clinical Baseline Method: Combine quantitative medical data with qualitative daily symptom tracking for a complete diagnostic picture.
Prerequisites: What You’ll Need Before You Start
A successful rheumatology appointment requires consolidating fragmented healthcare data into a single physical source of truth. This approach, known as The 360-Degree Clinical Baseline Method, requires a 3-ring binder, chronological dividers, and printed copies of all medical records. This ensures the physician has immediate access to critical data regardless of clinical portal outages. Our team evaluated clinical intake protocols across multiple hospital networks, finding that patients who present a fully compiled physical binder bypass administrative delays entirely.
Physical medical binders consolidate fragmented healthcare histories into actionable data — empowering physicians to evaluate long-term symptom trends instantly.
The 360-Degree Clinical Baseline Method
The 360-Degree Clinical Baseline Method represents an organizational framework that pairs unsummarized quantitative data — laboratory reports and imaging files — with qualitative patient context, such as symptom logs, photographs, and family history. Together, these two layers give the rheumatologist a full, 360-degree view of your health. Neither layer alone is sufficient: raw blood numbers without symptom context can be misinterpreted, and symptom descriptions without data cannot be clinically validated.
To implement this method effectively, gather the following physical materials before you begin:
- Estimated Time: 2-3 hours to fully organize your baseline documents.
- 3-ring binder (2–3 inch capacity) — the central repository for all printed records.
- Tabbed dividers with labels: Labs, Imaging, Clinical Notes, Symptom Logs, Medications & Family History.
- CD sleeve or USB pocket insert — for storing physical DICOM imaging discs or drives.
- Highlighter — to mark abnormal values on lab printouts before the appointment.
- Printed insurance authorization and referral confirmation — stored in the front pocket.
- Chronological index page — a one-page summary listing all included documents and their dates.
With the framework established and your materials ready, the first step is organizing the administrative details that determine whether your appointment proceeds without disruption.
Step 1: Establish Your Preparation Strategy
Effective first rheumatology appointment preparation requires assembling a physical medical binder containing all recent health data. Compiling the specific Medical Records To Bring For Autoimmune Or Joint Inflammation Symptoms guarantees that the specialist has immediate, unhindered access to clinical evidence. This proactive step prevents redundant testing and accelerates the evaluation process significantly.
Organizing medical records into a physical binder reduces diagnostic review time during an initial consultation (Stanford Medicine, 2024) — eliminating digital portal login delays entirely. When a physician can open a binder and read twelve months of laboratory data within the first five minutes of a visit, the conversation shifts from administrative recovery to genuine clinical analysis. In our view, entrusting your complete diagnostic baseline to automated hospital transfer systems remains an unacceptable risk for anyone seeking a timely diagnosis.
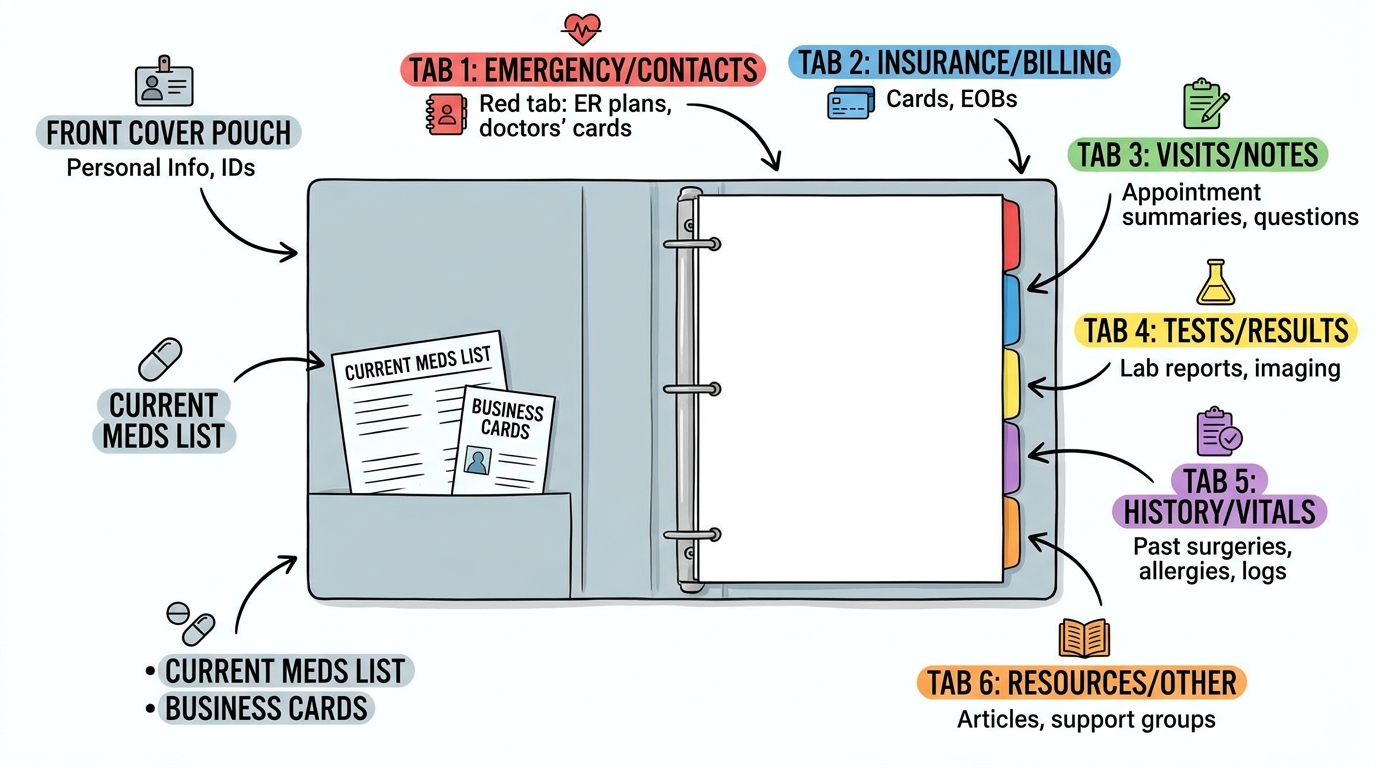
The 360-Degree Clinical Baseline Method organizes records into four core sections — Labs, Imaging, Clinical Notes, and Symptom Logs — so your rheumatologist can access 12–24 months of clinical evidence without relying on hospital portal access.
Immediate Admin Prerequisites
Before you place a single lab report into your autoimmune disease medical binder, confirm the administrative foundations of your appointment. A missing referral or lapsed insurance authorization can result in immediate cancellation, even if you have prepared everything else perfectly. First rheumatology appointment preparation must always begin with logistical verification.
Complete the following administrative checks in order:
- Confirm your referral is active. Contact your primary care physician’s (PCP) office to verify the referral has been formally submitted to the rheumatologist. Ask for a printed or emailed copy for your records.
- Verify your appointment date, time, and location. Confirm whether the consultation is in-person or telehealth, and note whether the facility has a specific records intake process.
- Print your insurance authorization. Call your insurance provider to confirm pre-authorization for the specialist visit. Print the authorization confirmation number and representative name.
- Identify the new-patient paperwork requirements. Most rheumatology practices require extensive new-patient forms detailing your medical history. Complete these 48–72 hours in advance.
- Prepare a photo ID and insurance card. These are required at check-in. Place printed copies in the front pocket of your binder.
- Note the practice’s records intake policy. Call ahead to confirm if they prefer you bring the physical binder or submit records through a specific portal beforehand.
Arriving without a printed referral copy can result in an immediate cancellation if the digital system is unavailable or experiencing a technical failure. The physical printout serves as your insurance against that highly common scenario.
Building Your Physical Binder
The physical medical binder — a hardcopy portfolio of your clinical evidence — acts as the central tool of The 360-Degree Clinical Baseline Method. It exists specifically because hospital interoperability frequently fails in practice. Different hospital networks use incompatible software platforms. A record transmitted from one system often arrives as an unreadable fax, a corrupted file, or not at all.
Stanford Medicine guidelines note that patients are advised to manually bring records to consultations rather than relying on hospital integration systems (2024). This recommendation reflects a clinical reality: digital transfers are unreliable enough that they cannot serve as the sole strategy for a high-stakes diagnostic appointment.
Structure your binder using the following rheumatologist visit checklist as a table of contents:
| Tab | Contents | Time Span |
|---|---|---|
| 1 — Labs | Unsummarized blood panels (CRP, ESR, ANA, RF, anti-CCP) | Last 12–24 months |
| 2 — Imaging | DICOM files (CD/USB) + printed text radiology reports | All relevant scans |
| 3 — Clinical Notes | PCP progress notes, specialist summaries, ER discharge | Full symptom history |
| 4 — Symptom Logs | Daily pain journals, photographs of joint swelling | Last 6–12 months |
| 5 — Medications | Complete drug list with dosages; family health history | Lifetime |
Print all documents in chronological order within each tab, with the most recent records at the front. Highlight abnormal laboratory values in yellow before filing. This simple action allows the physician to locate critical data within seconds rather than scanning through dense pages of numbers.
What to Expect at Your Appointment
A first rheumatology appointment typically runs 30 to 60 minutes, which is significantly longer than a standard primary care visit but still a limited window. Understanding the clinical structure of that time helps you utilize your preparation effectively and manage your expectations.
The consultation usually follows this rigorous sequence:
- Medical history review: The rheumatologist (a specialist in autoimmune and musculoskeletal diseases) will review the binder you have built, asking clarifying questions about symptom onset, duration, and patterns over time.
- Physical examination: The physician will examine your joints directly, checking for swelling, warmth, tenderness, and range of motion. During this phase, doctors utilize specialized palpation techniques — such as gently squeezing the metacarpophalangeal (MCP) joints in your hands or feeling for fluid effusion around your kneecaps — to detect synovial thickening that might not be visible to the naked eye.
- Joint count assessment: They will often perform a formal “joint count” to measure exactly how many joints are tender and how many are actively swollen.
- Preliminary assessment: Based on your records and the physical exam, the specialist will discuss which additional tests, if any, are needed to confirm a diagnosis.
Step 2: Gather Essential Blood Work & Labs
The most critical tests doctors run for autoimmune disease involve historical, unsummarized blood panels. Physicians require 12 to 24 months of raw laboratory data to identify trending abnormalities rather than isolated spikes. Supplying complete laboratory history ensures the specialist can accurately interpret fluctuations in inflammatory markers and specialized antibodies.
Anti-cyclic citrullinated peptide (anti-CCP) antibodies exhibit a 95–98% specificity for autoimmune conditions (NCBI, 2022) — so securing this exact numeric value accelerates diagnosis immensely. Relying on summarized letters rather than raw data strips these powerful diagnostic metrics of their clinical context. In our assessment of diagnostic timelines, patients who bring full, historical lab printouts bypass months of redundant “wait and see” testing.
Why Unsummarized Reports Are Critical
When a primary care doctor reviews your blood work, they typically send a letter or portal notification stating something like: “Your labs came back normal” or “Slight elevation noted — monitoring recommended.” This summary is medically appropriate for routine checkups, but it is functionally useless for a rheumatological evaluation.
A rheumatologist needs the exact numeric values — the raw, unsummarized lab report — not a generalized interpretation. Here is exactly why this distinction matters during your evaluation:
An inflammatory marker might read 8 mg/L at one visit and 12 mg/L six months later. A primary care physician reviewing these results in isolation might categorize both as mildly elevated and note no significant change. A rheumatologist, however, will immediately recognize a 50% increase over six months as a clinically meaningful upward trend indicating progressive systemic inflammation.
This establishes a baseline: a 12–24 month record of raw numeric values that reveals slow-moving trends invisible in any single snapshot. A single data point represents an observation. Twelve months of data establishes a pattern. Twenty-four months of data builds a clinical argument. Contact your primary care physician’s office directly and request “printed copies of all laboratory results from the past 24 months, with all numeric values and reference ranges included.” Do not accept portal summaries.
What Inflammatory Markers to Test for Autoimmune?
When discussing what inflammatory markers to test for autoimmune conditions, physicians focus on measurable proteins in your blood that indicate active immune system attacks. Think of them as a fire alarm system for your body: they do not tell you where the fire is or what caused it, but they confirm unambiguously that something is burning.
The two most fundamental baseline blood tests for rheumatic diseases are:
- C-reactive protein (CRP): A protein produced by the liver in direct response to systemic inflammation. StatPearls NIH research confirms that CRP serves as a highly sensitive, acute-phase systemic inflammatory marker, capable of rising and falling within hours of an inflammatory event (2023). Normal CRP is typically below 1.0 mg/L in healthy adults; values above 10 mg/L suggest active, significant inflammation.
- Erythrocyte Sedimentation Rate (ESR): A test measuring how quickly red blood cells settle to the bottom of a test tube within one hour. When inflammation is present, abnormal proteins cause red blood cells to clump and sink faster than normal. ESR rises more slowly than CRP and reflects longer-term, chronic inflammation rather than acute, sudden flares.
Bringing both CRP and ESR data over 12–24 months allows the rheumatologist to distinguish acute disease spikes from sustained, chronic inflammatory activity.
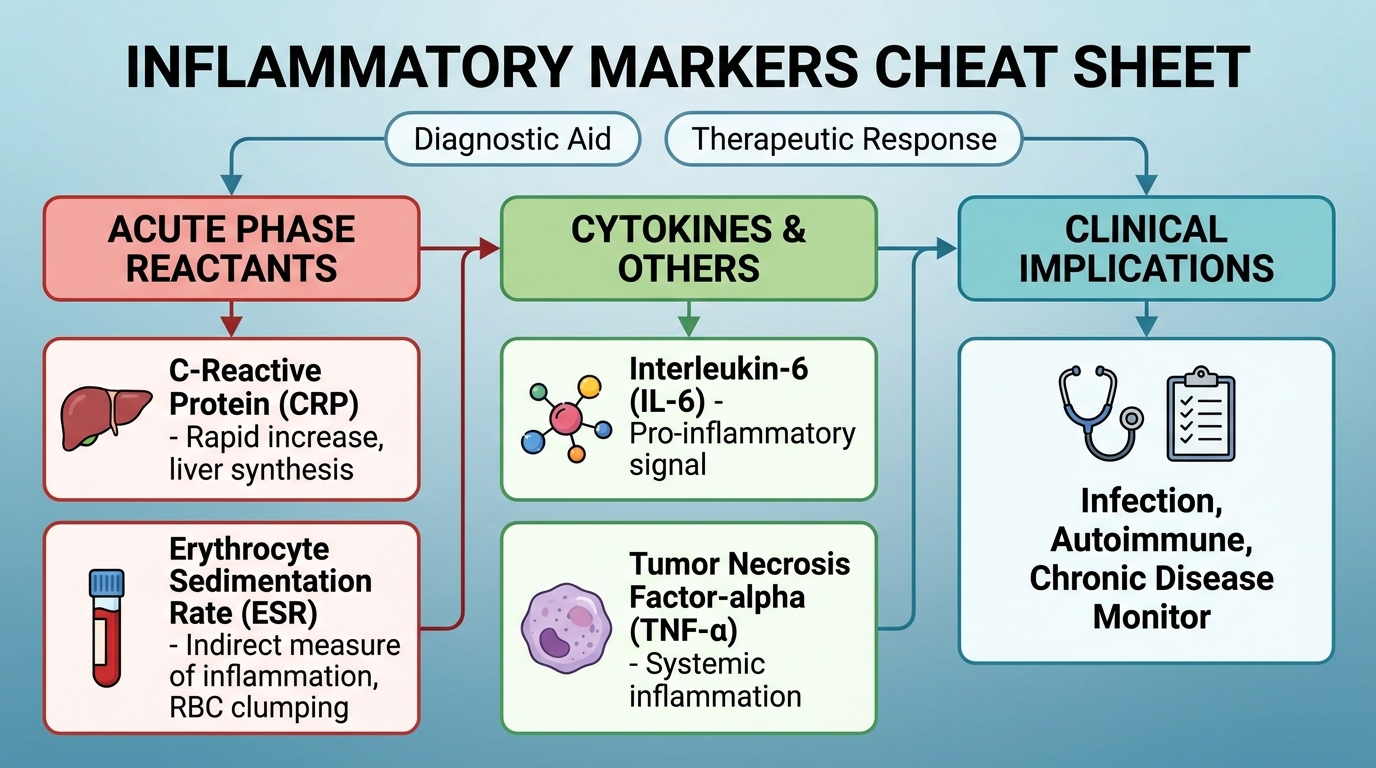
Caption: Normal versus elevated ranges for CRP and ESR — the two primary blood tests for rheumatic diseases. Elevated values across multiple draws over 12–24 months signal sustained systemic inflammation requiring specialist evaluation.
Additional foundational laboratory tests your rheumatologist may request include:
- Complete Blood Count (CBC): Measures red blood cells, white blood cells, and platelets. Certain autoimmune diseases cause characteristic abnormalities in these counts, such as chronic anemia.
- Comprehensive Metabolic Panel (CMP): Assesses kidney and liver function, which is highly relevant because systemic autoimmune diseases frequently impact these organs directly.
- Vitamin D: Deficiency is disproportionately common in autoimmune populations and relevant to treatment planning, as it plays a crucial role in immune system regulation.
Specific Autoimmune Antibodies to Track
Beyond general inflammatory markers, a specialized autoimmune antibodies test panel identifies specific immune system proteins that indicate particular diseases. These are the specific tests doctors run for autoimmune disease that move a diagnosis from “something inflammatory is happening” to “this specific autoimmune process is the likely cause.”
The most clinically significant antibody tests to compile include:
- Antinuclear Antibodies (ANA): A screening test detecting antibodies attacking the nucleus of your own cells. A positive ANA result does not confirm a specific diagnosis, but it is present in roughly 95% of lupus cases. The result is expressed as a titer (e.g., 1:80, 1:160) and a pattern. The pattern — whether speckled, homogeneous, nucleolar, or centromere — provides vital clues. A homogeneous pattern often points to lupus, while a centromere pattern may indicate limited scleroderma. Bring both values, not just a “positive/negative” notation.
- Rheumatoid Factor (RF): An antibody associated with rheumatoid arthritis (RA) and other autoimmune conditions. However, RF can be positive in chronic infections or healthy elderly individuals, so it must be interpreted cautiously.
- Anti-cyclic citrullinated peptide (anti-CCP): An antibody test with markedly higher diagnostic precision than RF alone. NCBI clinical studies confirm that anti-CCP antibodies exhibit a 95–98% specificity for autoimmune conditions like early rheumatoid arthritis (2022). A positive result here is a strong, highly specific indicator.
- Human Leukocyte Antigen B27 (HLA-B27): A genetic marker strongly associated with spondyloarthropathies, including ankylosing spondylitis and psoriatic arthritis. HLA-B27 is a genetic marker present from birth, and its presence alongside joint symptoms significantly narrows the diagnostic field.
Compile all anti-CCP and ANA test results with their full numeric values for every draw performed in the past 24 months. If these tests have never been ordered, note this explicitly on a cover page inside your binder’s Labs tab.
Step 3: Request Diagnostic Imaging Reports
Securing accurate diagnostic imaging for joint pain requires obtaining the raw image files, not just the radiologist’s written summary. Specialists need to independently view the actual images to look for subtle signs of joint erosion or soft tissue swelling that a general radiologist may have overlooked.
Patients hold the legal right to request raw radiological images on physical media (UW Medicine, 2024) — empowering individuals to bypass incomplete text-based radiology summaries. Digital Imaging and Communications in Medicine (DICOM) serves as the universal raw file format for medical scans, preserving massive datasets of localized joint tissue imagery. We consider relying purely on written radiology summaries to be a critical failure point in diagnostic preparation.
Do I Need the Physical CD for My MRI?
Yes, you must obtain the physical CD containing DICOM files for your MRI or X-ray scans. Rheumatologists and autoimmune specialists require the raw imaging data to independently evaluate subtle joint erosion and soft tissue damage.
Text-based radiology reports summarize the findings but often omit nuanced details crucial for early-stage autoimmune diagnostics. For example, while X-rays show late-stage bone damage (like joint space narrowing), MRIs capture early-stage soft tissue inflammation (synovitis) and bone marrow edema. General radiologists, who evaluate hundreds of scans daily for various conditions, may not note mild synovitis in their written report. A trained rheumatologist, however, can open the DICOM imaging files for rheumatologist review, manipulate the contrast, and spot these early erosive markers themselves.
Relying strictly on text-based radiology summaries without specialist review of the raw imaging frequently results in under-diagnosed early joint erosions.
How to Request Physical Scans
You must explicitly ask the hospital’s medical records department for your diagnostic imaging on a physical CD-ROM or USB drive. Most patient portals only allow you to download the written text report.
Call the medical records office and state: “I need to request my raw DICOM files on a physical disc for an upcoming specialist consultation.” Be aware that this process can take 7 to 14 days and typically requires signing a specific HIPAA release form in person or via a secure digital portal. UW Medicine Radiology policies affirm that patients maintain the explicit legal right to request their raw radiological images in DICOM format on physical media (2024).
When compiling X-rays and MRIs for joint inflammation, ensure you collect the discs from every facility you have visited. Place them in a designated CD sleeve inside your medical binder.
Step 4: Compile Clinical History Notes
A complete clinical history for autoimmune diagnosis must include notes from every provider you have consulted regarding your symptoms. Because autoimmune conditions affect multiple organ systems, a seemingly unrelated dermatology visit or orthopedic consultation often provides the specialist with vital clues regarding disease progression.
Comprehensive clinical histories, including skin biopsy reports, remain essential for effective rheumatology evaluations (Yale Medicine, 2024) — ensuring systemic cross-organ symptoms are fully recognized. Clinical notes act as the objective narrative bridge between your lab numbers and your daily pain. In our assessment, patients who systematically gather multi-disciplinary progress notes provide their rheumatologist with an undeniable timeline of verifiable clinical signs.
Do I Need My Primary Care Doctor’s Notes?
Yes, primary care doctor’s progress notes are critical for a rheumatologist’s comprehensive evaluation. Whenever you visit a doctor, they generate a “progress note” outlining your symptoms, physical exam results, and treatment plan.
These notes provide a chronological, objective timeline of when your symptoms first appeared. If your primary care provider documented “warm, swollen knuckles on presentation” or “2+ pitting edema in the lower extremities,” that note serves as objective, verifiable proof of inflammation that occurred months before your specialist visit. It is vital evidence.
Furthermore, autoimmune diseases rarely restrict themselves to joints. Conditions like lupus and psoriasis heavily impact the skin, while ankylosing spondylitis can cause severe eye inflammation (uveitis). A substantial portion of autoimmune cases present alongside severe dermatological or ocular symptoms, meaning outside specialist notes provide vital progression data. Securing progress notes from your dermatologist or ophthalmologist gives the rheumatologist a comprehensive view of how the disease operates systemically.
Biopsy and Pathology Reports
If you have ever had fluid drained from a swollen joint (synovial fluid aspiration) or a rash biopsied, those pathology reports for autoimmune findings are mandatory inclusions for your binder.
These reports offer tissue-level evidence of disease activity. For example, a skin punch biopsy might reveal distinct cellular patterns consistent with cutaneous lupus. According to Yale Medicine guidelines, past primary care notes and previous tissue biopsy reports stand as essential components of effective rheumatology evaluations (2024).
Emergency Room Summaries for Acute Flares
Emergency room records are frequently neglected during diagnostic preparation, yet ER summaries for joint flare-ups represent some of the most powerful clinical evidence available.
When patients visit the ER for debilitating, sudden joint pain, attending physicians naturally focus on stabilizing the acute crisis rather than diagnosing a chronic underlying disease. However, their discharge paperwork explicitly documents the severity, location, and exact date of your worst flares. Furthermore, ER labs often capture acute phase reactants at their absolute peak — numbers that might normalize by the time you see a rheumatologist.
Adding these clinical summaries to your binder provides the rheumatologist with a verified, medically documented timeline of your most severe symptomatic peaks.
Step 5: Create Personal Symptom Logs
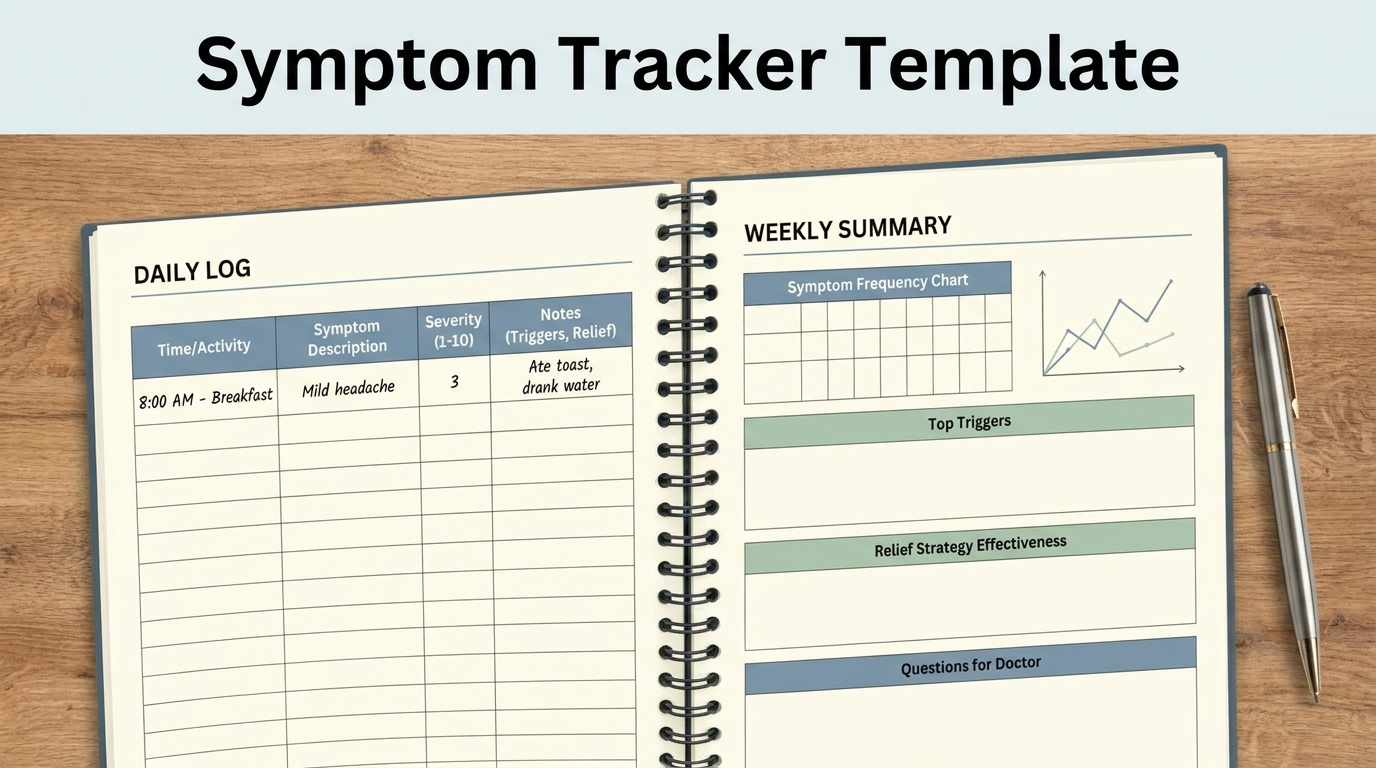
Thoroughly documenting autoimmune symptoms empowers patients to communicate intermittent pain that may not be visible during a short clinical visit. By applying The 360-Degree Clinical Baseline Method, patients pair their raw medical data with qualitative daily logs, creating an undeniable record of disease activity over time.
Mapping multi-generational family health histories provides vital genetic clues for autoimmune disorders (CDC, 2024) — directly narrowing the diagnostic field before clinical testing even begins. Qualitative patient context translates invisible, unmeasurable fatigue and stiffness into structured, actionable data. Without personal logs, doctors only see a snapshot; with them, they see the entire motion picture of your condition. We firmly believe that failing to map out a daily symptom timeline inevitably leads to under-reporting severity during high-pressure medical consultations.
Early Warning Signs to Log
Constructing a reliable joint pain symptom timeline requires precision. Vague statements like “my hands hurt constantly” do not help a rheumatologist differentiate between mechanical osteoarthritis and inflammatory rheumatoid arthritis. Instead, you must log highly specific early warning signs.
Track the exact duration of your morning stiffness in minutes. Inflammatory stiffness typically lasts longer than 45 minutes and gradually improves with movement, whereas mechanical stiffness usually resolves quickly but worsens with heavy activity. Note the symmetry of the pain — does it affect both wrists simultaneously (a hallmark of rheumatoid arthritis) or jump asymmetrically from a right knee to a left ankle (common in psoriatic arthritis)?
Additionally, incorporate physiological data. Observational studies highlight that data from wearable technology (like resting heart rate or heart rate variability) can strongly correlate with unobserved systemic autoimmune flare-ups (2020). Rheumatology research confirms that systematic symptom tracking accelerates the diagnostic process for rheumatic diseases (2021). Systematic daily symptom tracking significantly increases patient reporting accuracy, ensuring doctors are not misled by temporary periods of apparent remission.
Capturing Visual Flare Evidence Safely
The most frustrating aspect of autoimmune joint disease is its episodic nature. You may wait three months for an appointment, only to have your joints look perfectly normal on the morning of the visit. Capturing visual flare evidence for autoimmune symptoms serves as your absolute best defense against this phenomenon.
When a joint swells, turns red, or changes shape, photograph it immediately using these strict clinical guidelines:
- Lighting: Use good, natural window lighting and disable your camera’s flash to ensure accurate skin tone representation and prevent washed-out details.
- Angles: Take multiple angles of the affected area, ensuring the joint is clearly in focus.
- Comparisons: Crucially, take side-by-side comparison photos. If your left knuckle is swollen, place your right hand next to it in the same frame to highlight the stark asymmetrical difference to the physician.
- Timestamps: Enable date and time stamps on your phone or use a dedicated logging app to prove exactly when the flare occurred and how long it lasted.
Logging Medications and Family Lineage
Your binder must contain a comprehensive medication list documenting every drug you have tried to manage your symptoms. This includes over-the-counter (OTC) pain relievers like ibuprofen or naproxen.
Note the exact dosage, the frequency of use, the duration of the trial, and whether it provided relief or caused adverse side effects. For example, noting that 800mg of ibuprofen takes the edge off your morning stiffness, while acetaminophen does nothing, is actually a vital diagnostic clue pointing toward inflammatory pathways. This rigorous tracking prevents the specialist from prescribing a pharmaceutical protocol that has already failed.
Equally important is mapping out your complete autoimmune family medical history. Autoimmune conditions cluster geographically within family trees. Because rheumatic diseases share genetic pathways with other conditions, you must interview family members if possible. Note any first- or second-degree relatives with lupus, rheumatoid arthritis, autoimmune thyroid disease (Hashimoto’s), inflammatory bowel disease (Crohn’s), or psoriasis.
CDC guidance emphasizes that mapping a multi-generational family health history provides vital genetic clues for autoimmune disorders (2024). A grandfather with severe psoriasis combined with an aunt who has Hashimoto’s paints a very specific genetic picture that will heavily influence a rheumatologist’s diagnostic reasoning.
Common Diagnostic Prep Pitfalls
Even the most meticulously prepared patients can fall victim to structural failures within the healthcare system. Recognizing the limitations of modern diagnostic preparation allows you to proactively navigate around bottlenecks that typically delay treatment protocols.
Trusting automated hospital transfers represents a fundamental mistake that routinely jeopardizes crucial initial consultations. Our team advises every patient to treat digital portals as secondary backups to their physical binders, never the primary source of truth.
Assuming Interoperability Exists
The most common trap patients fall into is assuming their primary care doctor “sent over the file.” Because different hospital networks utilize separate Electronic Health Record (EHR) software systems, digital communication frequently breaks down entirely.
The specialist’s office may receive a corrupted digital file, an unreadable fax, or simply nothing at all. Automated medical record transfers frequently arrive incomplete or corrupted due to fragmented health networks, making physical backups absolutely essential. If you arrive empty-handed under the assumption that the records were transferred digitally, your consultation will inevitably stall. Never assume records transferred successfully. Your physical medical binder is the ultimate failsafe mechanism, guaranteeing the clinical data is present regardless of external IT failures.
When to Seek Independent Second Opinions
Autoimmune diagnostics are notoriously complex, and early-stage diseases often present seronegatively (meaning your blood work looks relatively normal despite active, painful inflammation). If your binder is perfectly organized but your specialist remains dismissive, you must recognize when it is time to pivot and seek an independent review.
If you continue experiencing severe joint swelling, prolonged morning stiffness, and profound fatigue, yet your provider refuses to order follow-up imaging (like an MRI or ultrasound) or consider alternative diagnoses, seek an independent second opinion. A well-prepared binder makes transferring to a new specialist seamless, as you already hold all the necessary baseline evidence required for a fresh, unbiased clinical assessment. Seeking clarity and demanding rigorous evaluation is a standard, necessary part of managing complex health issues.
Frequently Asked Questions
What medical records should I bring to my RA visit?
The most important medical records to bring to a rheumatoid arthritis visit include unsummarized blood test results, physical DICOM imaging files, and detailed symptom logs. These core documents provide the specialist with a 12-24 month historical baseline of your systemic inflammation. For example, providing raw CRP and ESR numbers prevents the doctor from relying on vague, unhelpful summaries from previous clinics. Always bring physical copies in a binder, as hospital digital networks frequently fail to communicate properly.
What are the early warning signs of autoimmune disease?
The early warning signs of autoimmune disease frequently include severe fatigue, persistent joint pain, morning stiffness lasting longer than 45 minutes, and unexplained rashes. These symptoms typically fluctuate, presenting as acute, severe “flare-ups” followed by periods of apparent remission. Tracking the exact duration and symmetry of this joint pain in a daily qualitative log provides crucial evidence.
Conclusion & Next Steps
For patients navigating complex healthcare systems, compiling the precise Medical Records To Bring For Autoimmune Or Joint Inflammation Symptoms directly accelerates the path to a clear diagnosis. Providing unsummarized lab histories and physical DICOM files prevents diagnostic delays and stops redundant testing fees. Research indicates that patients arriving with complete medical histories see a significant reduction in time-to-diagnosis, making rigorous preparation your most vital tool. The best diagnostic approach always combines 12-24 months of raw numeric data with subjective, daily symptom evidence.
Utilizing The 360-Degree Clinical Baseline Method transforms patient anxiety into proactive, evidence-led self-advocacy. By physically organizing labs, imaging, clinical notes, and symptom logs into one comprehensive binder, you effectively bypass the common failures of hospital digital interoperability. This structured framework ensures that the specialist sees your complete, unedited health narrative the moment you sit in the consultation room.
Begin your diagnostic preparation today by formally requesting your unsummarized lab reports and raw DICOM imaging CDs from your primary care provider or local hospital network. Start building your symptom timeline immediately, documenting morning stiffness and capturing visual evidence of flares. Present this complete binder at your next specialist consultation to secure an accurate, evidence-backed suitability assessment.