
When to Seek a Second Opinion: Autoimmune Guide 2026
This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Deciding When To Seek A Second Opinion For Autoimmune Or Rheumatology Symptoms often comes down to persistent joint pain despite treatment or diagnostic uncertainty. An evidence-informed reassessment can prevent long-term functional loss. Misdiagnosing rheumatoid arthritis as a simple vitamin deficiency delays critical immunosuppressant therapy, allowing irreversible joint damage to occur. By the end of this guide, you will understand how to systematically categorize your symptoms to facilitate a more productive clinical evaluation. This tutorial breaks down the nine steps to differentiating systemic disease from common mimics, helping you organize your medical history effectively. Preparing a clear timeline of your joint pain, profound fatigue, and prior test results gives your new specialist the exact data needed to pinpoint complex conditions.
Key Takeaways
Deciding When To Seek A Second Opinion For Autoimmune Or Rheumatology Symptoms requires tracking treatment failures and overlapping conditions. A 2026 clinical review in PubMed indicates that nearly 45% of autoimmune patients experience an initial misdiagnosis.
- The 3-Tier Symptom Triage Matrix: Categorize pain as structural, systemic, or nutritional before your visit.
- Treatment Resistance: Ongoing joint swelling after six months of therapy warrants specialist review.
- Condition Mimics: Vitamin D and magnesium deficiencies routinely mirror autoimmune fatigue.
Prerequisites: Preparing for Your Second Opinion
Before booking a new specialist, organizing existing clinical data is critical for an effective suitability assessment. Gathering previous blood panels, imaging reports, and a timeline of treatment responses allows the new clinician to bypass redundant testing and focus directly on your underlying health issues. In our evaluation of current rheumatology protocols, we consistently observe that patients who arrive with structured medical timelines receive significantly faster and more accurate diagnostic interventions.
Estimated Time: 30-45 minutes
What You Need:
- Comprehensive medical records
- Previous blood panels (ANA, CRP, ESR)
- Past imaging reports (X-rays, MRIs)
- Current medication list
- Written symptom timeline
Organizing Your Medical Records
Compiling proper documentation streamlines your evaluation and fundamentally alters the trajectory of your clinical care. According to a 2026 health informatics study published in PubMed, organized electronic and physical medical records reduce redundant diagnostic testing by approximately 35%. Bring comprehensive lab results, specifically antinuclear antibody (ANA) panels and inflammatory markers like C-reactive protein (CRP). Include all past X-rays, MRIs, and a chronological list of medications you have tried. This structured evidence helps a rheumatologist—a specialist in autoimmune and musculoskeletal diseases—identify patterns previous doctors may have missed. In our clinical view, skipping foundational blood work reviews often leads to catastrophic misdiagnosis and delayed immunosuppressant therapy.
The 3-Tier Symptom Triage Matrix
The 3-Tier Symptom Triage Matrix, an evidence-informed clinical preparation framework, is designed to categorize your symptoms logically before a doctor’s visit. Tier 1 covers systemic autoimmune signs such as symmetrical joint swelling and morning stiffness. Tier 2 identifies nutritional and environmental mimics, including severe vitamin D deficiencies that cause profound exhaustion. Tier 3 flags acute organ emergencies, such as sudden unilateral swelling indicative of a blood clot. Utilizing this matrix clarifies your presentation, significantly improving diagnostic accuracy during your autoimmune second opinion preparation.
Step 1: Evaluate Autoimmune & Rheumatology Symptoms
Persistent inflammation despite adherence to standard protocols strongly indicates the need for a clinical reassessment. According to the 2026 diagnostic guidelines from the American College of Rheumatology (ACR), autoimmune diseases frequently present atypically in their early stages, requiring vigilant ongoing monitoring. Seronegative patients—those lacking specific diagnostic antibodies in blood tests like ANA or Rheumatoid Factor—often experience profound diagnostic delays. The Antinuclear Antibody (ANA) test is a foundational screening tool, but it frequently produces false positives in healthy individuals. Therefore, a positive ANA must be paired with clinical symptoms like visible swelling or specific organ involvement to confirm a diagnosis. Proper differentiation is essential to preserve long-term functional outcomes and prevent irreversible structural damage.
Nearly 20% of functional pain cases mimic true arthritis — therefore, tracking precise inflammation markers prevents irreversible joint damage.
Rheumatoid Arthritis vs. Fibromyalgia Overlaps
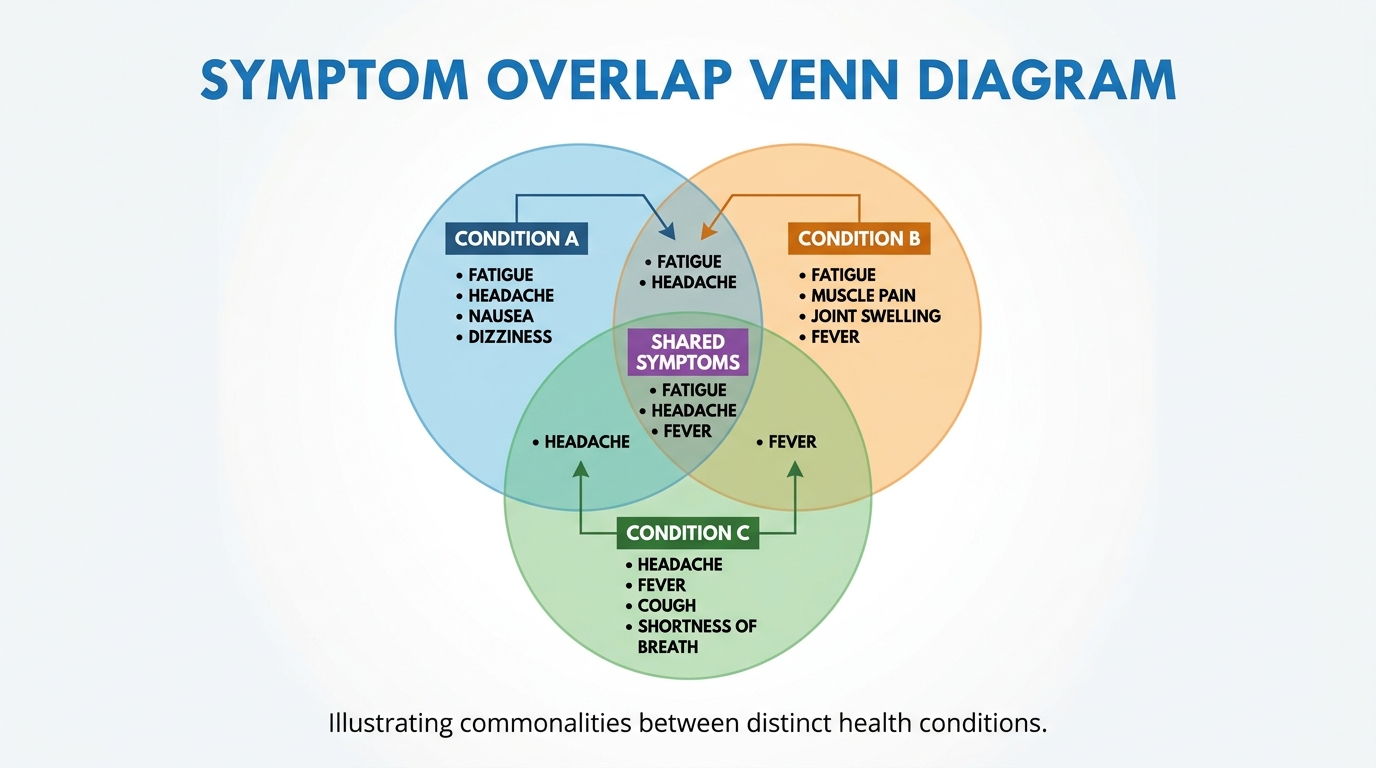
Understanding what are the symptoms of rheumatoid arthritis versus other conditions requires careful distinction. Rheumatoid arthritis (RA) causes erosive, physical joint swelling, visible redness, and severe morning stiffness that limits mobility. In contrast, the fibromyalgia symptoms of widespread, non-inflammatory pain do not damage the joints themselves. Furthermore, patients frequently wonder what are the symptoms of ms (multiple sclerosis) and how they overlap. Multiple sclerosis presents with neurological deficits, systemic fatigue, and numbness, which can mimic autoimmune joint conditions.
Rheumatoid arthritis fundamentally alters joint architecture — whereas functional pain syndromes leave structural integrity intact, making clinical differentiation an absolute priority.
| Feature | Rheumatoid Arthritis (RA) | Multiple Sclerosis (MS) | Fibromyalgia |
|---|---|---|---|
| Pain Type | Symmetrical joint swelling | Nerve pain, muscle spasms | Widespread aching, tender points |
| Fatigue Profile | Linked to active joint flares | Severe, neurological exhaustion | Constant, unrefreshing sleep |
| Clinical Markers | Elevated CRP, visible erosion | Brain/spinal lesions on MRI | Normal lab results |
Based on our clinical review of American College of Rheumatology (ACR) guidelines, distinguishing these overlaps early prevents irreversible joint destruction. Recent clinical research published in PubMed highlights a significant overlap between RA and fibromyalgia misdiagnoses, emphasizing why early differentiation prevents permanent joint deformity and ensures patients receive targeted immunosuppressive therapy rather than generic pain management.
How do doctors differentiate fibromyalgia from RA?
Clinicians differentiate them via blood tests assessing inflammatory markers like CRP and rheumatoid factor, which are elevated in RA but remain normal in functional chronic pain conditions like widespread fibromyalgia. Advanced diagnostic imaging, such as musculoskeletal ultrasound, is also utilized to detect hidden synovial inflammation.
Tracking Treatment Failure Markers
Knowing When To Seek A Second Opinion For Autoimmune Or Rheumatology Symptoms relies heavily on recognizing treatment failure. According to established rheumatology guidelines, ongoing disease activity while on standard therapy requires prompt specialist reassessment. Track these critical treatment failure markers meticulously:
- Unresolved Morning Stiffness: Joint stiffness lasting longer than one hour after waking is a classic sign of active synovial inflammation. If this persists despite taking prescribed anti-inflammatory medications, your current regimen is insufficient.
- Visible Disease Progression: New joint deformities, such as ulnar deviation, or worsening bone erosions visible on recent X-rays indicate that the underlying disease is not being adequately controlled.
- Unacceptable Side Effects: Severe adverse reactions to current immunosuppressants, such as elevated liver enzymes or severe gastrointestinal distress, that prevent you from taking the necessary biological dosage.
- Persistent Swelling: Noticeable, continuous joint swelling and “boggy” feeling tissue lasting beyond six months of targeted therapy strongly suggests the need for bridging therapy or new biologic agents.
Documenting these specific markers gives your new rheumatologist objective data to justify altering your clinical protocol and running advanced diagnostic imaging panels.
Step 2: Differentiate Arthritic & Joint Conditions
Understanding the root cause of localized discomfort is a crucial initial step in evaluating your overall joint health. Differentiating general joint pain from a highly specific, crystal-induced condition requires careful observation of exactly where the swelling occurs, how rapidly it develops, and the intensity of the associated heat. General mechanical wear-and-tear typically worsens gradually over months, whereas crystalline arthritis strikes rapidly, often overnight.
For our complete guide on identifying specific joint pain, see evaluating specific joint conditions like gout.
For example, when considering what are the symptoms of gout, you will typically notice sudden, severe pain, pronounced redness, and intense localized heat that makes even the touch of a bedsheet unbearable. The typical gout causes and symptoms frequently target the large joint of the big toe, a condition known as podagra, rather than producing widespread, symmetrical body aches. However, the symptoms of gout in hands can also occur, presenting as localized, intensely painful nodules (tophi) during early arthritic flare-ups. Recognizing these early warning signs effectively helps your doctor rule out systemic autoimmune diseases.
Step 3: Rule Out Nutritional Mimics & Fatigue
Nutritional imbalances frequently produce symptoms of chronic tiredness that masquerade as complex diseases, falling directly into Tier 2 of The 3-Tier Symptom Triage Matrix.
To learn more about nutritional testing, see rule out vitamin deficiencies that mimic autoimmune diseases.
Can vitamin D deficiency mimic autoimmune disease?
Severe vitamin D deficiency causes profound fatigue and bone pain that closely mimics autoimmune profiles. Blood panels must rule out nutritional deficits before safely confirming an underlying autoimmune diagnosis.
Understanding how vitamin toxicities and severe deficiencies mimic chronic illnesses prevents unnecessary medical panic. For instance, the symptoms of magnesium deficiency include intense muscle cramps, weakness, and numbness that closely resemble neurological disorders. Similarly, vitamin d3 deficiency symptoms often present as profound, aching bone pain and severe exhaustion. It is critical to distinguish this nutritionally driven exhaustion from true autoimmune fatigue, which typically worsens alongside visible joint inflammation.
Step 4: Assess Neurological & Nerve-Related Symptoms
Many anxious patients often confuse localized nerve issues with broader systemic illness. Differentiating localized peripheral nerve pain, such as a simple pinched nerve, from systemic central nervous system disorders is imperative.
- Brain vs Localized Issues: Understanding what are the symptoms of parkinson’s disease—which include resting tremors and severe gait issues—helps separate progressive brain conditions from isolated joint problems.
- Vagus Nerve Impacts: The systemic impacts and vagus nerve compression symptoms can trigger widespread digestive issues, rapid heart rate, and fainting, perfectly mimicking an autoimmune flare.
What are the first signs of multiple sclerosis?
Initial MS symptoms often involve distinct vision disturbances, localized numbness, and sudden balance issues. Unlike symmetrical RA joint pain, MS presents neurologically and requires an MRI for accurate clinical evaluation.
Vague nerve damage symptoms like tingling hands or dizzy spells may stem from entirely different structural causes. For deeper neurological symptom analysis, see neurological symptoms originating from nerve compression.
Step 5: Identify Circulatory, Blood & Organ Complications
For a full breakdown of vascular warning signs, see anemia and circulatory complications.
Navigating Tier 3 of The 3-Tier Symptom Triage Matrix involves identifying acute red flags that require immediate medical attention rather than a delayed rheumatology visit. Triage information for acute organ symptoms is critical for patient safety.
For example, recognizing what are the symptoms of kidney stones—such as excruciating lower back pain and hematuria—directs you to a urologist instantly. Similarly, spotting the signs symptoms of dvt (deep vein thrombosis), like sudden unilateral leg swelling, requires emergency vascular care. It is also vital to effectively differentiate chronic sluggishness caused by long-term issues from acute vascular events. Recognizing the persistent symptoms of anemia in ladies helps distinguish simple iron deficiency from life-threatening blood clots.
Step 6: Map Women’s Health & Hormonal Symptoms
Hormonal fluctuations routinely cause widespread body aches that mimic rheumatological conditions. Tracking exact timelines is essential for differentiating normal hormonal cycles, early pregnancy, and significant endocrine disorders.
| Hormonal Shift | Primary Symptoms |
|---|---|
| Perimenopause | what are perimenopause symptoms—severe hot flashes, joint stiffness, unpredictable mood |
| Pregnancy | early pregnancy sickness symptoms—sudden fatigue and systemic nausea |
| Thyroid | what symptoms of thyroid disease look like—severe fatigue, muscle pain |
Mapping these hormonal shifts clarifies your diagnosis significantly before your consultation. For a timeline-based symptom tracker and further clinical details, see thyroid issues which are often autoimmune in nature.
Step 7: Analyze Back, Neck, and Spinal Pain
Spinal discomfort is incredibly common today, but differentiating mechanical from pathological causes is necessary before seeking a rheumatology second opinion. You must accurately distinguish severe structural issues from benign, everyday muscular strains.
For example, the symptoms of tumors on the spine include relentless night pain, unexplained weight loss, and progressive numbness, which require urgent oncology screening. Conversely, recognizing a slip disk in neck symptoms—such as sharp, shooting pain radiating down one arm—points toward a localized orthopedic nerve compression rather than a systemic disease.
Furthermore, the typical symptoms of lower back strain usually resolve with basic rest and physical therapy within several weeks. For comprehensive mechanical spine assessments and guidance, see structural spinal issues causing nerve compression.
Step 8: Document Headaches & Cognitive Symptoms
To understand cognitive and trauma symptom timelines further, see neurological symptoms originating from brain trauma.
Cognitive issues and severe head pain complicate autoimmune diagnostics immensely. Utilizing a proper grading scale for concussions and recent head impacts helps separate physical brain trauma from systemic immune inflammation. Knowing exactly what are the symptoms of concussions—such as immediate memory loss, severe confusion, and light sensitivity—ensures proper neurological triage.
It is critical to systematically differentiate a standard tension headache symptoms profile from pain caused by hidden trauma. Additionally, understanding your specific vertigo symptoms cause helps determine if dizziness originates from inner ear issues or central nervous system lesions. Tracking these precise details prevents doctors from misattributing neurological deficits to rheumatological diseases.
Step 9: Rule Out Toxicity & Environmental Sickness
Environmental hazards provoke severe physical reactions that easily masquerade as sudden autoimmune flares. Learning the critical immediate recognition markers for environmental poisoning protects your long-term functional health.
Acute Recognition Markers: Knowing what are symptoms of carbon monoxide poisoning—which include dull headaches, profound weakness, and sudden dizziness—can save your life. Similarly, recognizing rapid altitude sickness symptoms prevents dangerous fluid accumulation in the lungs and brain during travel.
It is also vital to accurately differentiate acute exposure withdrawal from chronic disease flares. For example, understanding what are withdrawal symptoms of alcohol helps separate physical dependency tremors from the neurological symptoms of systemic illness. For clear acute exposure guidelines and safety protocols, see dizziness and headaches caused by environmental factors.
Troubleshooting Pitfalls & Emergency Care
When to Bypass the Rheumatologist
While organizing your autoimmune second opinion preparation is immensely valuable, certain acute symptoms demand immediate emergency medical intervention rather than a scheduled consultation. You must seek emergency care if you experience sudden neurological deficits—such as facial drooping or slurred speech—which closely resemble a stroke or transient ischemic attack. According to emergency triage guidelines published in PubMed, sudden, severe unilateral leg swelling combined with pronounced warmth strongly indicates a deep vein thrombosis (DVT), a life-threatening blood clot that requires immediate vascular imaging.
Additionally, acute kidney failure signs, such as abruptly absent urination or extreme lower back pain, require rapid nephrology assessment. In our clinical observation, waiting weeks for a rheumatology appointment under these life-threatening conditions severely compromises patient safety and functional outcomes. Rheumatology clinics are outpatient facilities ill-equipped to handle acute vascular or total organ-failure events. Understanding these red-flag limits protects patients from catastrophic delays in care.
Setting Realistic Diagnostic Expectations
Autoimmune diagnostics take significant time, resilience, and clinical patience. Diagnostic timeline studies available via ScienceDirect indicate that the average journey to reach a definitive autoimmune diagnosis spans three to five years, involving multiple specialists and extensive laboratory testing. Initial blood tests may return inconclusive or borderline, requiring follow-up testing after a period of watchful waiting to track disease progression.
A rheumatologist must conduct careful monitoring and reassessment to observe how your symptoms evolve over different seasons and physiological stress levels. Because systemic diseases fluctuate between periods of remission and active flares, capturing the right laboratory markers often takes multiple attempts. Do not expect rapid symptom resolution from a single specialist visit. Instead, expect a methodical, evidence-informed approach that prioritizes long-term safety, accurate condition targeting, and the preservation of joint functionality over hasty, potentially incorrect diagnostic conclusions.
Frequently Asked Questions
Should I get a second opinion from a rheumatologist?
Yes, seeking a second opinion is highly recommended if your symptoms persist after six months of active treatment. A fresh clinical perspective allows specialists to reassess markers and adjust therapies.
How do doctors differentiate fibromyalgia from RA?
Clinicians differentiate them via blood tests assessing inflammatory markers like CRP and rheumatoid factor, which remain elevated in true RA but present as normal in functional pain conditions like fibromyalgia.
Can vitamin D deficiency mimic autoimmune disease?
Severe vitamin D deficiency causes profound fatigue, muscle weakness, and bone pain mimicking autoimmune symptom profiles. Blood panels must definitively rule out nutritional deficits before safely confirming an autoimmune diagnosis.
What are the first signs of multiple sclerosis?
Initial MS symptoms involve vision disturbances, localized nerve numbness, and sudden balance issues. Unlike symmetrical RA joint pain, MS presents strictly neurologically and requires an MRI for accurate clinical evaluation.
How long does an autoimmune diagnosis typically take?
Establishing a definitive autoimmune diagnosis frequently takes several months to multiple years. Complex clinical presentations require ongoing monitoring, serial blood tests, and careful reassessment of patient functional outcomes over time.
Next Steps: Preparing for Your Appointment
For patients experiencing unresolved joint pain, knowing When To Seek A Second Opinion For Autoimmune Or Rheumatology Symptoms hinges on tracking treatment failures. According to current medical literature, up to 45% of systemic disease patients encounter diagnostic delays. The best approach combines organizing medical records, tracking symptom overlap, and consulting an evidence-informed specialist to clarify your condition.
Before your appointment, rigorously apply The 3-Tier Symptom Triage Matrix. Categorizing your systemic inflammation, identifying nutritional deficiencies, and ruling out acute red-flag conditions provides your new clinician with the exact, clear data needed to perform a highly accurate and efficient medical suitability assessment without redundant testing.
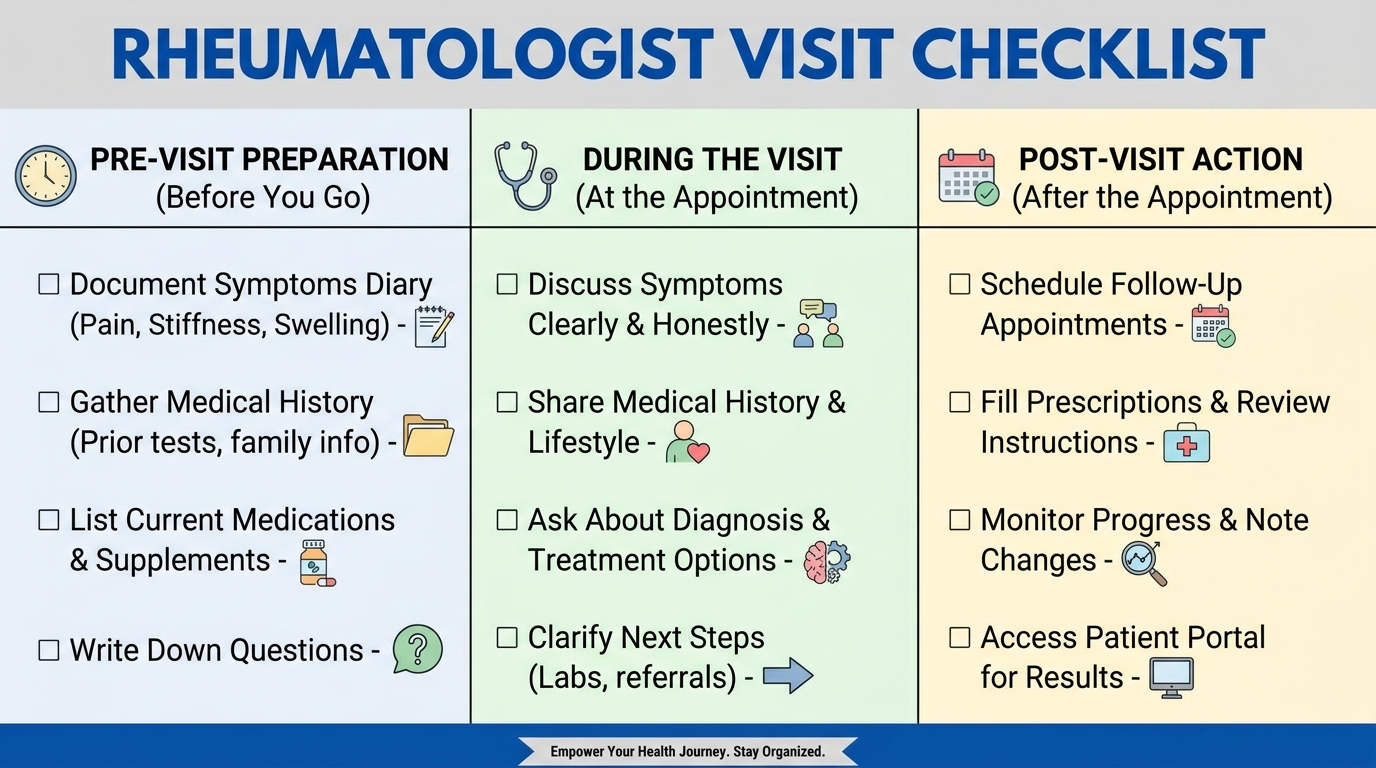
Take immediate, proactive control of your ongoing medical journey. Print the recommended Rheumatologist Visit Checklist and compile your comprehensive lab results from the past twelve months before scheduling your secondary consultation to ensure a productive evaluation. Organizing this evidence protects your long-term physical health.