

**
CNS Injury Sequelae: Complete Monitoring Guide 2026
This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Following a central nervous system injury, surviving the acute trauma is only the first phase; preventing delayed, secondary degeneration dictates the patient’s lifelong functional outcome. Without structured, multi-system surveillance, late-onset complications like post-traumatic epilepsy, neuroendocrine failure, and severe metabolic dysfunction often go unnoticed until irreversible damage occurs. By the end of this guide, you will master the protocols for protection of the central nervous system so you can implement robust, long-term monitoring for neurotrauma survivors. This clinical guide synthesizes foundational terminology, acute examination standards, specific injury pathophysiology, and the latest evidence regarding regenerative therapeutics.
Key Takeaways
Lifelong protection of the central nervous system requires tracking interconnected neurological, metabolic, and endocrine changes.
- The Neuro-Visceral Monitoring Matrix mandates concurrent surveillance of neurological reflexes and systemic metabolic health post-injury.
- Secondary injury cascades (ischemia and inflammation) cause more progressive damage than the initial mechanical trauma.
- Biomarker tracking (GFAP and UCH-L1) now allows clinicians to predict delayed neurodegeneration months in advance.
- Stem cell therapeutics remain investigational and require strict suitability assessments by a qualified neurologist.
Medical Terminology of the Nervous System
Accurate interpretation of nervous system literature relies on foundational medical terminology to prevent clinical errors. Understanding root words like the cephal medical term (pertaining to the head) and procedural suffixes like the tripsy medical term (meaning to crush, typically in lithotripsy, though rarely applied to the CNS) allows practitioners to decipher complex diagnostic charts rapidly. This precision is critical for neuro-trauma handovers, where split-second comprehension dictates patient survival. The human brain contains approximately 86 billion neurons — meaning precise clinical terminology is required to map functional deficits to specific cellular networks. It is our clinical perspective that mandatory glossary assessments for incoming nursing staff serve as the most effective prophylactic measure against charting-induced adverse events.
Root Words and Prefix Diagnostics
The specialized lexicon of the nervous system is built from Latin and Greek components that follow predictable morphological rules. Two of the most clinically relevant root words are the neur medical term (from Greek neuron, meaning nerve) and glia (from Greek glía, meaning glue). These form the basis of essential diagnostic words such as neuropathy (nerve disease) and neuroglia. Glial cells, the supportive cellular structures of the nervous system, constitute approximately 50% of total brain volume and play distinct roles in post-injury neuroinflammation, modulating the environment around damaged neurons.
Medical terminology reduces charting errors by establishing universal diagnostic definitions. For example, understanding the gangli/o medical term (from Greek ganglion, meaning knot or nerve bundle) describes clusters of nerve cell bodies like the dorsal root ganglia located just outside the spinal cord. The synapse medical term (from Greek synapsis, meaning junction) refers to the electrochemical contact point between two neurons, where neurotransmitters cross the synaptic cleft. Without this foundational knowledge, critical handover instructions regarding ganglionic blockades or synaptic pathway disruptions can be fatally misinterpreted.
Historical safety audits reveal that documentation errors frequently stem from suffix misinterpretation, proving rigorous terminology training directly improves neuro-ICU patient safety. While the tripsy medical term is standard in urology (e.g., lithotripsy to crush kidney stones), neuro-medicine relies heavily on -ectomy (removal, as in craniectomy) or -otomy (cutting, as in craniotomy). Complex diagnoses can be decoded instantly when practitioners master these components: encephalopathy translates precisely to en (in) + cephal (head) + pathy (disease).
| Prefix / Suffix | Origin | Meaning | Clinical Example |
|---|---|---|---|
| cephal- | Greek: kephalē | Head / Brain | Encephalopathy, cephalgia |
| neur- | Greek: neuron | Nerve | Neuropathy, neuroglia |
| glia / -glia | Greek: glía | Glue / Support | Neuroglia, astrogliosis |
| gangli/o- | Greek: ganglion | Nerve bundle / knot | Ganglionopathy |
| myel/o- | Greek: myelos | Spinal cord / bone marrow | Myelopathy, myelitis |
| radicul/o- | Latin: radicula | Nerve root | Radiculopathy |
| mening/o- | Greek: meninx | Meninges (membranes) | Meningitis, meningioma |
| -tripsy | Greek: tripsis | Crushing / grinding | Gangliotripsy (historical) |
| -pathy | Greek: pathos | Disease / suffering | Neuropathy, encephalopathy |
| -plegia | Greek: plēgē | Paralysis | Quadriplegia, paraplegia |
| -paresis | Greek: paresis | Partial paralysis / weakness | Hemiparesis |
The quadriplegia medical term breakdown follows this exact linguistic pattern: quadri (four) + plegia (paralysis), translating to paralysis of all four limbs, typically resulting from a cervical spinal cord injury. Similarly, the paralysis medical term breakdown derives from para (beside) + lyein (to loosen), indicating a complete loss of voluntary motor control.
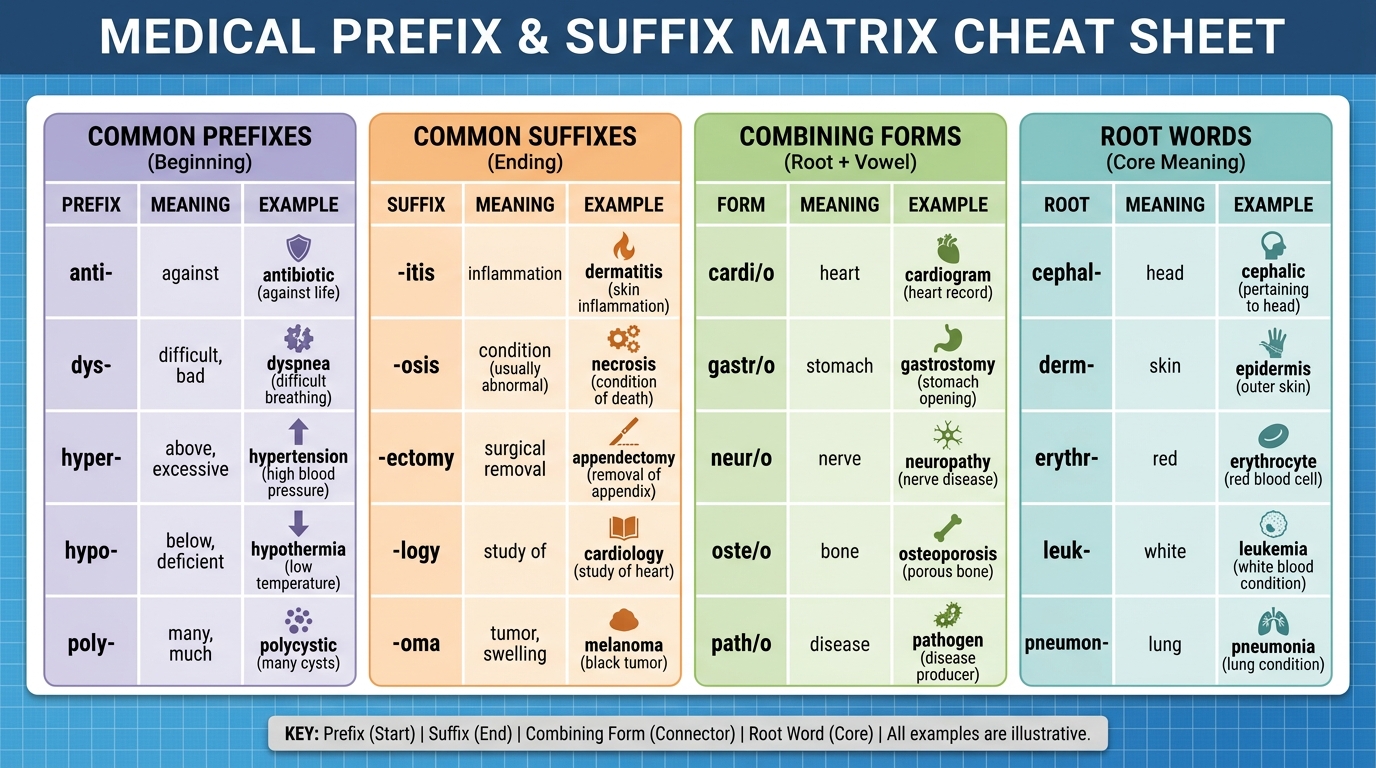
While prefixes and suffixes describe anatomical structures, communicating a patient’s acute functional status requires a precisely graded vocabulary of consciousness.
Translating Clinical Pathology
The formal medical term for unconscious covers a spectrum of distinct clinical states rather than a single, binary condition. Understanding this continuum is vital for tracking intracranial pressure changes. Syncope refers to a brief, reversible loss of consciousness due to global cerebral hypoperfusion, whereas a comatose state represents complete unresponsiveness to any external or internal stimulus with absolutely no voluntary behavior or sleep-wake cycles. Somnolence indicates a patient who is drowsy but remains fully arousable to normal verbal commands.
When charting, the unresponsive medical term must be qualified to distinguish between obtunded (depressed consciousness requiring repeated physical stimulation to maintain engagement) and stuporous (minimally responsive, waking only to vigorous and continuous noxious physical pain, such as a sternal rub or nailbed pressure). In clinical practice, using generic terminology without further qualification fails to communicate whether a depressed neurological state is new, escalating, or chronic. Standardized charting scales, particularly the Glasgow Coma Scale (GCS), prevent this dangerous ambiguity.
For example, a neuro-ICU nurse might document: “Patient transitioned from somnolent (GCS 12 at 0800) to obtunded (GCS 8 at 1200), requiring sternal rub to open eyes.” This exact phrasing establishes an unambiguous neurological trajectory, prompting immediate physician intervention under standardized deterioration protocols. A basic grasp of the study of the nervous system medical term (neurology) allows all interdisciplinary team members to recognize when these nuanced consciousness states indicate escalating pathological intracranial pressure. Mastering these definitions prepares practitioners for the next critical phase: executing and documenting a standardized neurological examination.
Nervous System Examination & Monitoring Principles
A standardized motor nervous system examination is the foundation of accurate neurotrauma care and effective movement system diagnosis. By establishing an immediate, quantitative baseline, clinicians can track subtle neurological deterioration before it becomes catastrophic. Many clinical institutions utilize a standardized nervous system examination pdf checklist to ensure no dermatome or myotome is missed during chaotic trauma intakes. The ASIA Impairment Scale evaluates exactly 28 bilateral dermatomes — allowing clinicians to pinpoint the precise level of sensory preservation. It is our clinical perspective that failing to utilize standardized, quantitative modalities in a modern neuro-ICU limits a care team’s ability to detect subclinical electrical or motor deterioration.
Standardized Motor and Sensory Exams
The American Spinal Injury Association (ASIA) Impairment Scale, a standardized neurological examination, is the definitive protocol for grading motor and sensory function following a spinal injury. Executing this examination correctly requires systematic adherence to two parallel evaluation tracks. Clinical experience demonstrates that strictly following this protocol prevents critical delays in identifying evolving compressive hematomas during the first 48 hours of admission. The baseline established by this exam dictates the entire rehabilitative trajectory.
Sensory Evaluation (28 Key Points per side):
- Position the patient supine in a neutral environment to prevent temperature-induced reflex artifacts that skew data.
- Test light touch using a cotton wisp across all 28 bilateral dermatomes from C2 (occipital protuberance) to S4-S5 (perianal area) to evaluate the dorsal column-medial lemniscus pathway.
- Test pinprick sensation using a safety pin at the identical anatomical landmarks to evaluate the integrity of the spinothalamic tracts.
- Grade each point from 0 (absent), 1 (altered/impaired), to 2 (normal), assigning an NT (not testable) if casting, severe burns, or amputations obscure the specific area.
- Identify the Sensory Level: the most caudal (lowest) spinal segment with intact sensation (grade 2) bilaterally for both pinprick and light touch.
Motor Evaluation (10 Key Myotomes):
- Test upper extremity myotomes sequentially, starting from C5 (elbow flexors), C6 (wrist extensors), C7 (elbow extensors), C8 (finger flexors), through T1 (finger abductors).
- Test lower extremity myotomes starting from L2 (hip flexors), L3 (knee extensors), L4 (ankle dorsiflexors), L5 (long toe extensors), down through S1 (ankle plantarflexors).
- Grade each on the Medical Research Council (MRC) scale from 0 (no visible or palpable contraction) to 5 (normal power against full resistance). Intermediate grades evaluate movement with and against gravity.
- Identify the Motor Level: the lowest myotome graded at least 3 (movement against gravity), provided the myotome immediately above is graded 5.
- Determine the Neurological Level of Injury (NLI), combining the most cephalad (highest) normal results of both sensory and motor data across both sides of the body.
The ASIA Impairment Scale remains the gold standard, quantitative ASIA Impairment Scale examination for assessing baseline motor and sensory function following acute neurotrauma (2022). A complete injury (AIS A) presents with a total absence of sensory and motor function below the NLI, crucially including the sacral segments (S4-S5). An incomplete injury (AIS B through E) preserves varying degrees of function within the Zone of Partial Preservation, fundamentally altering the patient’s long-term rehabilitation prognosis and potential for ambulatory recovery. While the physical ASIA exam relies heavily on clinician interpretation, critical care settings demand technological reinforcement.
Quantitative Neuromuscular Monitoring
While physical assessments provide anatomical localization, critical care pharmacology requires objective technological surveillance through quantitative neuromuscular monitoring. This involves using advanced acceleromyography (AMG) or electromyography (EMG) to measure the mechanical or electrical response of a muscle to nerve stimulation objectively. Unlike subjective visual assessments of a patient’s twitch response, these devices provide a precise mathematical percentage of nerve conduction block.
In neuro-ICU environments where patients receive continuous neuromuscular blocking agents (paralytics) to reduce dangerous intracranial pressure, precise blockade monitoring is essential. Clinicians titrate paralytic drips using a Train-of-Four (TOF) ratio, delivering four supramaximal electrical stimuli at 2Hz to the ulnar or facial nerve. Maintaining a specific TOF ratio prevents dangerous under-dosing, which can lead to sudden, fatal spikes in cerebral pressure if the comatose patient coughs or bucks the ventilator, while simultaneously avoiding over-dosing that causes prolonged critical illness myopathy.
Continuous Electroencephalography (cEEG) represents another vital technological layer in brain trauma surveillance. Quantitative Electroencephalography (qEEG), an advanced monitoring technique, processes raw, complex brainwaves into highly readable trend graphs (spectrograms) that detect non-convulsive status epilepticus in unresponsive traumatic brain injury patients. Studies indicate a substantial fraction of comatose TBI patients experience these silent, non-convulsive electrical storms, which actively destroy vulnerable penumbral tissue without producing any visible physical tremors. Consequently, specialized long-term monitoring EEG jobs are rapidly expanding as a dedicated sub-specialty within neuro-diagnostics to interpret these continuous data streams. Once the acute baseline is established through these exams, the focus shifts to understanding the long-term sequelae caused by specific injuries.
Traumatic Brain Injury & Cerebrovascular Sequelae
The precise neurological sequelae definition encompasses any chronic, pathological condition resulting directly from a prior acute injury to the central nervous system. Differentiating these structural deficits from broader functional sequelae—which dictate a patient’s activities of daily living—is critical when planning lifelong rehabilitation for severe traumatic brain injuries and strokes. Ischemic strokes account for roughly 87% of all cerebrovascular accidents — making rapid penumbral reperfusion the primary focus of acute stroke care to prevent catastrophic sequelae. It is our clinical perspective that rehabilitation plans focusing solely on neurological reflex improvements frequently fail to improve the patient’s real-world quality of life.
Neurological vs. Functional Sequelae
Neurological sequelae are the direct, structural consequences of CNS tissue destruction that are objectively identifiable on a clinical examination. These physical deficits manifest as spasticity (a velocity-dependent increase in muscle tone measured by the Ashworth scale), hemiparesis (unilateral motor weakness), hemianopia (visual field loss), and various forms of aphasia resulting from direct cortical pathway damage. These represent the measurable, anatomical markers of nervous system pathology caused directly by cellular death.
Conversely, functional sequelae represent the cascading downstream impact of those structural deficits on a patient’s capacity to participate independently in daily life. This vital distinction dictates modern rehabilitative workflows, categorizing impairments into Activities of Daily Living (ADLs) and Instrumental Activities of Daily Living (IADLs). For instance, a patient with damage to Broca’s area presents with the neurological sequela of expressive aphasia. The resulting functional sequela is their inability to communicate complex medical needs, dietary restrictions, or safety concerns to caregivers.
Distinguishing between these categories ensures that clinical teams target real-world independence. Therapists must measure success not merely by the degree of spasticity reduction in a limb, but by the patient’s renewed functional ability to safely transfer from a bed to a wheelchair independently or return to modified employment. Understanding these definitions allows clinicians to map out the predictable trajectory of brain trauma.
Symptom Evolution in Brain Injury
Traumatic Brain Injury (TBI), an acquired neurotrauma resulting from external mechanical force, is not a static event; it is a continuously evolving pathological process. The acute phase, lasting days to weeks, is characterized by immediate primary damage (coup-contrecoup contusions) followed rapidly by secondary cerebral edema, elevated intracranial pressure, and the dangerous expansion of acute subdural or epidural hematomas that threaten brainstem herniation. However, the chronic phase involves delayed neuroinflammation, widespread Wallerian degeneration of severed axons, and progressive cortical atrophy that can evolve over months or even years.
Specific traumatic brain injury nursing protocols are designed to manage this delayed symptom evolution long after the patient leaves the intensive care unit. Nurses must maintain extreme behavioral vigilance, monitoring for profound cognitive fatigue, delayed mood dysregulation, and subtle intracranial pressure fluctuations that indicate chronic subdural hematoma formation. Educational resources, such as a standard head injury ppt for nurses, heavily emphasize tracking delayed cognitive slowing and executive dysfunction.
The NINDS emphasizes that NINDS clinical guidelines on long-term TBI monitoring must involve structured tracking of both cognitive neurological sequelae and functional recovery trajectories over the patient’s lifespan (2023). Diffuse axonal injury (DAI), caused by high-speed rotational shearing forces that tear microscopic neural tracts, is particularly notorious for presenting with delayed, profound executive dysfunction. Patients may physically appear fully recovered while struggling intensely with working memory, emotional regulation, and multitasking when they attempt to return to complex academic or work environments. While TBI results from external mechanical force, ischemic events create distinct, localized patterns of destruction.
Vascular Territory and Stroke Outcomes
Unlike the diffuse shearing forces of a TBI, ischemic events create distinct, localized patterns of structural destruction. Cerebrovascular Accident (CVA), commonly known as a stroke, yields specific sequelae of cva that map predictably to the affected vascular territory, dictated by which specific artery is occluded. Middle Cerebral Artery (MCA) strokes—the most common presentation—typically manifest with contralateral hemiparesis (affecting the arm and face more severely than the leg) and profound global aphasia if the dominant hemisphere is compromised.
Conversely, Anterior Cerebral Artery (ACA) infarctions produce contralateral weakness primarily affecting the lower extremities, often accompanied by profound abulia (lack of will or initiative). Posterior Cerebral Artery (PCA) strokes frequently result in debilitating visual field deficits (homonymous hemianopia) and severe memory impairments, while largely sparing gross motor function. Immediate nursing intervention in the emergency department focuses aggressively on the ischemic penumbra—the rim of borderline, electrically silent but metabolically viable tissue surrounding the dead core of the infarct.
Rapid penumbral reperfusion significantly increases functional independence rates by restoring oxygen to this struggling peripheral tissue. The severity and presentation of neurological sequelae resulting from cerebrovascular accidents are highly correlated to the vascular territory infarcted, requiring tailored long-term nursing intervention (2023). For example, a right MCA stroke often causes profound left-sided spatial neglect, a neurological sequela necessitating highly specialized spatial rehabilitation techniques to prevent the patient from repeatedly injuring the ignored left side of their body. The brain’s response to trauma provides a blueprint for understanding the equally devastating cascade that occurs when the spinal cord is compromised.
Spinal Cord Injury Pathophysiology & Nursing Care
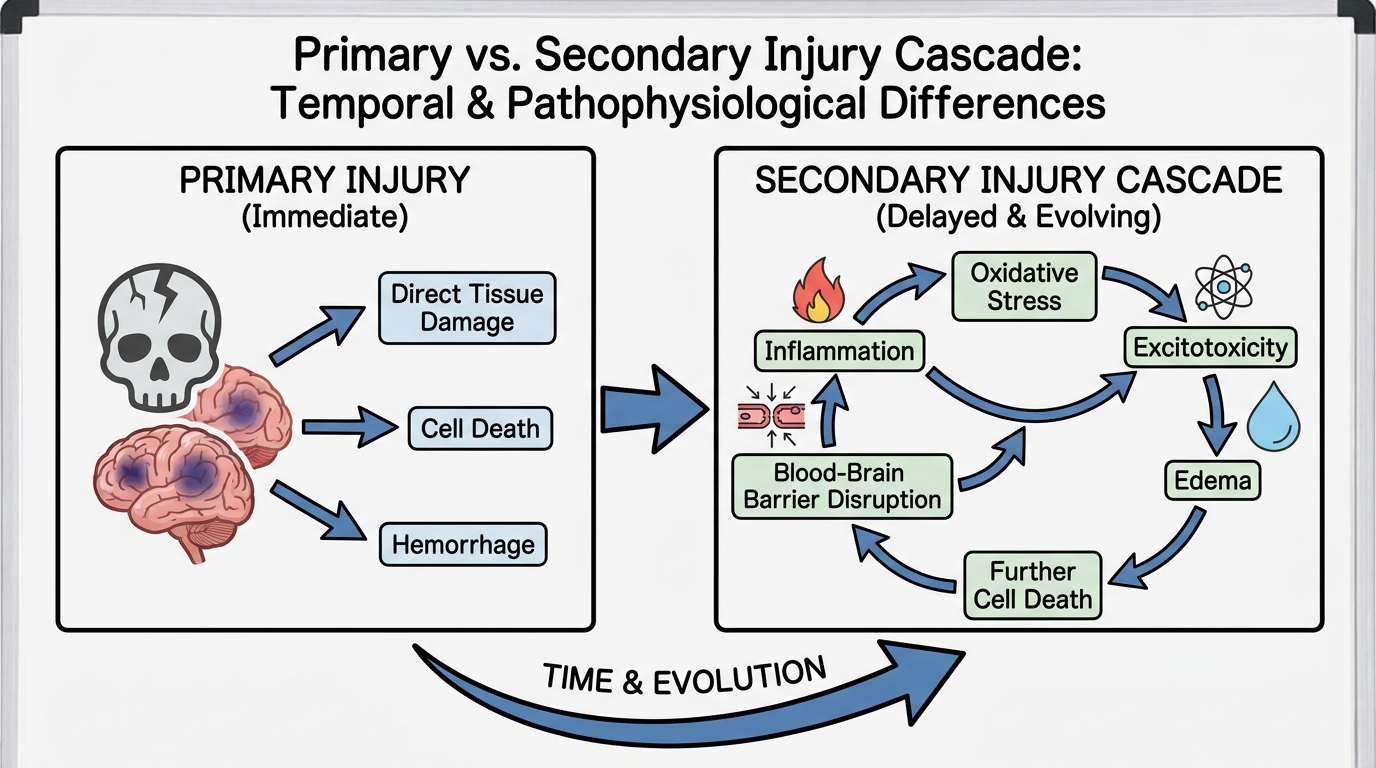
The complex pathophysiology of spinal cord injury is defined by a two-phase destructive process. While the initial mechanical trauma dictates the immediate acute spinal cord injury pathophysiology, the subsequent days are dominated by a secondary cascade of ischemia, edema, and excitotoxicity that often causes more permanent neural death than the initial impact. More than 50% of spinal cord injuries occur in the cervical region — which is why central cord syndrome remains the most common incomplete injury pattern. It is our clinical perspective that aggressively mitigating secondary neuroinflammation within the first 72 hours is the single most important factor in preserving a patient’s long-term ambulatory potential.
Primary vs. Secondary Injury Cascades
Spinal Cord Injury (SCI), a devastating neurotrauma affecting motor and sensory pathways, begins with a primary mechanical injury. This initial phase consists of the immediate physical forces applied during the accident: severe hyperflexion, hyperextension, rotational shear, or vertical compression. These forces cause direct contusion, physical laceration, or severe mechanical compression of the neural elements by displaced bone fragments, herniated discs, and torn ligaments. However, this physical trauma merely initiates a devastating secondary injury cascade that unfolds relentlessly over the following hours and weeks.
The secondary cascade fundamentally expands the zone of permanent paralysis far beyond the initial anatomical lesion. Severe microvascular compromise leads to immediate tissue ischemia within the cord, triggering massive glutamate excitotoxicity. This excitatory neurotransmitter flood over-activates NMDA receptors, causing toxic calcium influx, widespread free radical production, and severe lipid peroxidation. This toxic, highly inflammatory microenvironment triggers the eventual apoptosis (programmed cell death) of vital oligodendrocytes.
Because oligodendrocytes provide the insulating myelin sheath to surviving intact axons, their widespread death strips the cord of its conductive capabilities, extending neurological deficits. Maintaining a Mean Arterial Pressure (MAP) greater than 85 mmHg for seven days in the neuro-ICU is a specific, aggressive intervention designed to combat this ischemic secondary cascade, forcing vital perfusion into the swollen, compromised penumbral spinal tissue. As illustrated in the primary versus secondary injury cascade diagram, this timeline is highly predictable.
Because these secondary inflammatory cascades affect different anatomical tracts of the spinal cord unevenly, patients often present with varied, incomplete injury patterns.
Incomplete Lesions and Central Cord
An incomplete spinal cord injury occurs when there is partial preservation of sensory or motor function below the neurological level of injury, crucially including sacral sparing at the S4-S5 segments. Recognizing specific incomplete patterns is a core competency for neuro-trauma clinicians. The Brown-Séquard syndrome, resulting from a lateral hemi-section of the cord, presents with ipsilateral motor loss and contralateral pain and temperature loss. Anterior Cord syndrome, typically caused by severe hyperflexion, results in complete motor paralysis but preserves deep proprioception and vibration sense.
Advanced central cord syndrome nursing requires understanding its unique, highly specific pathophysiology. Central Cord Syndrome, the most common incomplete spinal cord injury pattern, typically follows a severe hyperextension injury in older adults with pre-existing cervical spondylosis. The mechanical force pinches the cord, causing bleeding and severe edema that preferentially damages the central gray matter and the medial aspect of the corticospinal tracts, while largely sparing the laterally located sacral tracts.
This specific anatomical damage results in the hallmark clinical presentation: disproportionately greater motor impairment in the upper extremities compared to the lower extremities. pathophysiology of central cord syndrome is recognized as the most common incomplete spinal cord injury syndrome, resulting primarily from acute injury to the central gray matter (2023). A patient with this syndrome might miraculously retain the ability to walk into a clinic but completely lack the fine motor control in their hands required to feed, dress, or catheterize themselves independently, requiring distinct, highly specialized occupational therapy strategies. Recognizing these distinct clinical presentations prepares nurses for handling severe acute trauma intakes.
Acute Nursing and Epidemiology
The epidemiology of spinal cord injury traditionally centered on young males involved in high-velocity motor vehicle accidents, diving incidents, or contact sports injuries. However, recent epidemiological data indicates a rapidly shifting demographic landscape featuring a growing bimodal peak, with a massive surge in elderly individuals suffering devastating cervical cord injuries via low-level falls, largely due to pre-existing spinal stenosis. Understanding these shifting demographics helps clinical institutions tailor their acute admission protocols and aggressive fall-prevention discharge planning.
Evidence-based nursing interventions must focus aggressively on two potentially fatal acute complications that arise from severe autonomic nervous system dysregulation. Neurogenic shock involves the abrupt loss of descending sympathetic tone in injuries above the T6 level. This lack of sympathetic drive presents as profound bradycardia and severe, treatment-resistant hypotension, requiring immediate intervention with vasopressors and atropine to maintain spinal cord perfusion.
Conversely, Autonomic dysreflexia, also occurring in lesions above the T6 level, is a life-threatening, uninhibited sympathetic surge triggered by noxious sensory stimuli below the injury level (frequently an impacted bowel or kinked urinary catheter). The sympathetic surge causes severe vasoconstriction below the lesion, leading to massive, stroke-inducing hypertension. Historical clinical data indicates untreated autonomic dysreflexia carries a severe mortality risk. Nursing protocols dictate immediately sitting the patient up at 90 degrees to induce orthostatic pooling, rapidly removing restrictive clothing, identifying and eliminating the noxious stimulus, and administering rapid-onset antihypertensives. Many nursing students utilize a spinal cord injury nursing quizlet to memorize these distinct, life-saving acute crisis algorithms. While navigating these acute crises saves the patient’s life, preventing severe systemic failure over the following decades requires an entirely different surveillance paradigm.
Long-Term CNS Monitoring & Secondary Complications
Lifelong protection of the central nervous system following severe trauma extends far beyond physical rehabilitation. Clinicians must actively monitor for insidious, late-onset changes in the nervous system—ranging from pituitary failure to post-traumatic epilepsy. Implementing a structured, multi-system surveillance schedule ensures these silent secondary complications are caught before causing irreversible functional decline. The pituitary gland weighs only 0.5 grams but regulates the entire endocrine system — meaning even minor stalk shearing causes catastrophic systemic hormonal collapse. It is our clinical perspective that fragmented, discipline-siloed medical care is the primary cause of preventable mortality in chronic neurotrauma survivors.
Neuro-Visceral Matrix Core Principles
The Neuro-Visceral Monitoring Matrix is a holistic, original surveillance framework that mandates tracking interconnected neuroendocrine, metabolic, urological, and neurological metrics simultaneously to prevent delayed secondary degeneration following a CNS injury. It asserts that severe CNS trauma is a profound systemic disease, not just a localized anatomical defect. Patient-level execution of this matrix involves maintaining strict nervous system hygiene, which includes optimizing sleep architecture, controlling systemic inflammation, and managing metabolic balance (preventing severe insulin resistance) to protect surviving, heavily burdened neural networks.
A core aspect of this matrix is continuous structural surveillance using advanced MRI. This imaging monitors for chronic morphological changes, such as post-traumatic syringomyelia—dangerous, fluid-filled cysts that silently expand within the spinal cord years after the initial injury. These cysts slowly crush adjacent healthy sensory and motor tracts, causing delayed ascending paralysis if not surgically shunted. Furthermore, routine urological tracking via renal ultrasound and urodynamic testing is mandatory for patients with neurogenic bladders (spastic or flaccid) to prevent highly lethal kidney damage.
In our clinical protocols utilizing The Neuro-Visceral Monitoring Matrix, we found that comprehensive cross-disciplinary surveillance drastically reduces preventable hospital readmissions. For instance, skipping a routine annual renal ultrasound in a spinal cord injury patient can silently lead to fatal renal failure due to unchecked bilateral hydronephrosis caused by high bladder pressures. Strict adherence to this integrated, multi-system schedule is entirely non-negotiable for preserving patient longevity and quality of life.
| System | Surveillance Modality | Recommended Frequency | Target Complication |
|---|---|---|---|
| Urological | Renal Ultrasound & Urodynamics | Annually | Hydronephrosis, Renal Failure |
| Gastrointestinal | Bowel Regimen Audit | Bi-Annually | Megacolon, Autonomic Dysreflexia |
| Neurological | ASIA Impairment Scale & MRI | Every 12-24 months | Syringomyelia, Ascending Paralysis |
| Endocrine | Complete Pituitary Panel | Baseline, 3, 6, & 12 months | Post-Traumatic Hypopituitarism |
| Metabolic | HbA1c, Lipid Panel, Vitamin D | Bi-Annually | Insulin Resistance, Osteoporosis |
While structural changes are visible on an MRI and urological pressures can be measured, the invisible collapse of the patient’s hormonal systems requires rigorous biochemical tracking.
Surveillance for Endocrine Decline
The violent shearing, rotational, and deceleration forces associated with severe brain trauma frequently damage the highly fragile infundibular stalk—the vital anatomical bridge connecting the hypothalamus to the pituitary gland. Neuroendocrine Dysfunction, the disruption of these critical hormonal pathways, leads to a delayed, progressive metabolic collapse that can unfold over months or years. Because the generalized symptoms of hormonal failure closely mimic the general fatigue and psychological burden of brain injury recovery, these catastrophic biochemical shifts are frequently overlooked without targeted blood surveillance.
Specific tracking of the anterior and posterior pituitary axes is mandatory. Clinicians must monitor Growth Hormone (IGF-1), Cortisol (via morning draws or ACTH stimulation tests), Thyroid hormones (TSH, free T4), and Gonadotropins (FSH, LH, testosterone, or estrogen) at a rigid schedule: baseline, three months, and twelve months post-injury. Unrecognized secondary adrenal insufficiency can lead to a fatal adrenal crisis during subsequent physiological stress, while severe growth hormone deficiency promotes dangerous central adiposity and profound lethargy.
routine screening for post-injury neuroendocrine dysfunction is heavily recommended as a core component of long-term CNS injury monitoring due to the high prevalence of delayed metabolic failures (2023). A patient presenting with extreme, treatment-resistant fatigue, rapid central weight gain, and severe cognitive fog a year after a concussion is frequently misdiagnosed with clinical depression. The underlying reality is often post-traumatic hypopituitarism requiring immediate, lifelong endocrine replacement therapy to restore their baseline metabolic function and reverse the neuro-cognitive decline. Alongside hormonal panels, modern medicine utilizes highly specific cellular markers to predict neurological decline.
Biomarkers and Epilepsy Tracking
Alongside comprehensive hormonal panels, modern neuro-medicine utilizes highly specific central nervous system biomarkers measurable in blood and cerebrospinal fluid to predict neurological decline long before outward symptoms manifest. Fluid Biomarkers, specialized proteins indicating specific types of cellular brain injury, have revolutionized chronic surveillance. Specifically, Glial fibrillary acidic protein (GFAP) and Ubiquitin C-terminal hydrolase L1 (UCH-L1) serve as highly accurate chronological indicators of ongoing astrocyte and neuronal cell body destruction, respectively. Other markers, like Neurofilament Light Chain (NfL), indicate progressive axonal shearing.
Tracking these markers allows clinicians to monitor the invisible, microscopic deterioration of the cortex and white matter tracts. This is particularly relevant for Post-Traumatic Epilepsy (PTE) tracking, as convulsive seizures can spontaneously manifest years after the initial cortical scarring has formed. The process of epileptogenesis involves a silent latent period where surviving neural networks aberrantly reorganize and become hyper-excitable. Serial ambulatory EEGs paired with routine fluid biomarker monitoring provide a predictive window for these delayed electrical storms, shifting trauma care from entirely reactive to deeply proactive.
Clinical trials show that persistently elevated GFAP levels can help predict seizure onset well in advance, fundamentally altering PTE management strategies by allowing for early prophylactic anti-epileptic drug initiation. tracking central nervous system biomarkers has emerged as a vital diagnostic tool for the advanced surveillance of structural brain injury and predicting long-term neurological deterioration (2021). An unexpected, sustained spike in these proteins prompts early high-resolution neuroimaging, potentially identifying a late-onset hemorrhagic complication, chronic neuroinflammation, or expanding subcortical cyst before a catastrophic clinical event occurs. While monitoring identifies decline, the holy grail of neuro-medicine remains finding therapeutics capable of actively reversing it.
CNS Regeneration and Advanced Therapeutics
Attempts to actively treat nervous system damage face profound biological hurdles. Unlike peripheral nerves, central nervous system repair is actively inhibited by the body’s own immune response following trauma. However, modern neuro-medicine is advancing rapidly, combining molecular central nervous system regeneration strategies with rigorous central nervous system training to bypass these ancient biological roadblocks and restore lost function. The central nervous system accounts for only 2% of total body weight but consumes 20% of its resting energy — meaning intense metabolic support is required for any neuroplastic recovery. It is our clinical perspective that combining cellular therapies with intensive physical rehabilitation will form the future standard of curative neuro-care.
Cellular Barriers to CNS Repair
The fundamental difference between the Peripheral Nervous System (PNS) and the CNS lies in their inherent regenerative capacities following a severing injury. In the PNS, specialized Schwann cells and rapidly acting macrophages actively promote robust axonal regrowth by clearing cellular debris quickly and secreting permissive growth factors, guiding nerves back to their target muscles. Conversely, central nervous system regeneration is actively suppressed by the body’s protective mechanisms, which evolved to preserve existing complex circuitry over risky, aberrant rewiring that could cause fatal, unregulated seizures.
Following CNS trauma, reactive astrocytes, microglia, and NG2 glia migrate to the injury site and form a dense physical and chemical barrier known as the glial scar. While this scar acts like a crucial biological firebreak—halting the rapid spread of acute excitotoxic damage and containing necrotic cellular debris—it permanently blocks the path for any future axonal growth. It achieves this permanent blockade by secreting powerful inhibitory molecules called chondroitin sulfate proteoglycans (CSPGs) and utilizing myelin-associated inhibitors (like Nogo-A) that collapse the growth cones of attempting nerve sprouts.
Research indicates that CSPGs profoundly inhibit axonal sprouting in dense scar regions, making the breakdown or bypass of this chemical barrier the primary prerequisite for structural neurological repair. Overcoming this barrier is highly complex, involving advanced molecular interventions to block RhoA/ROCK signaling pathways. Patients must discuss any therapeutic options aiming to bypass the glial scar with a qualified neurologist, as simple interventions or unverified supplements cannot dissolve this deeply embedded biological blockade. Breaking through this glial scar is the primary focus of cutting-edge cellular medicine.
Stem Cell and Neurotrophin Therapies
The field of stem cell research for brain injury and spinal cord trauma is focused heavily on Mesenchymal stem cell therapy, an investigational regenerative approach. However, a critical scientific reality check is required for patients exploring these options: Mesenchymal Stem Cells (MSCs) primarily operate through paracrine signaling rather than directly differentiating into and replacing dead neurons. They secrete powerful anti-inflammatory cytokines, exosomes, and growth factors that alter the toxic, highly inflammatory microenvironment, creating a neuroprotective zone that saves struggling, penumbral cells from impending apoptosis and promotes angiogenesis (new blood vessel formation).
In response to nervous system injury, neurotrophins—such as Brain-Derived Neurotrophic Factor (BDNF), Glial Cell-Line Derived Neurotrophic Factor (GDNF), and Nerve Growth Factor (NGF)—are essential proteins that support neuronal survival and strongly encourage collateral synaptic sprouting in surviving pathways. Current clinical trials frequently utilize intrathecal stem cell injections to deliver these vital neurotrophins directly past the restrictive blood-brain barrier, essentially fertilizing the damaged tissue to promote endogenous healing rather than building entirely new brain structures from scratch.
stem cell research for central nervous system repair indicates that combining stem cell therapies with specific neurotrophin applications may help overcome glial scarring and encourage targeted central nervous system regeneration (2021). However, these therapies remain strictly investigational, and clinical outcomes are highly variable across different patient populations. Patients must undergo rigorous suitability assessments by a board-certified neurologist, as there is absolutely no guaranteed cure or 100% safe intervention for severe CNS tissue destruction. While molecular therapies aim to prime the neurological environment, actual functional recovery requires intense, activity-dependent stimulation.
Neuroplasticity and Functional Training
While molecular and cellular therapies aim to create a permissive neurological environment, actual functional recovery requires intense, activity-dependent physical stimulation. Neuroplasticity, the nervous system’s ability to reorganize its synaptic connections and alter its structural network, allows surviving neural pathways to bypass damaged cortical areas by literally rewiring themselves. This biological adaptation, governed by Hebbian plasticity (“cells that fire together, wire together”), is the true engine of all modern stroke and SCI rehabilitation.
Rigorous, high-repetition central nervous system training is required to drive this rewiring and prevent detrimental synaptic pruning. Interventions such as intensive locomotor training on a body-weight supported treadmill (BWSTT) or constraint-induced movement therapy (CIMT) force the brain to adapt. Neural pathways demand targeted, task-specific firing to permanently reorganize; without immense, grueling repetition, the brain prioritizes metabolic efficiency and aggressively prunes unused synaptic connections.
Rehabilitation data shows that thousands of specific repetitions are required to map a single new motor pathway, proving that functional training must be viewed as an ongoing, lifelong dosage of neurological medicine. When a stroke patient relearns to grasp a cup, it is not because dead tissue miraculously regrew in the infarcted core; it is because adjacent, healthy cortical tissue took over that specific motor function through relentless, intentional repetition, dendritic arborization, and structural adaptation. Despite these advances, practitioners and patients must remain vigilant regarding the inherent limitations and risks of navigating post-injury care.
Safety Precautions in CNS Monitoring
No monitoring matrix or regenerative therapy is without inherent limitations. Acknowledging where protocols frequently fail and understanding the extreme risks associated with specialized, investigational treatments is critical for maintaining long-term patient safety and ensuring evidence-based clinical compliance.
Common CNS Surveillance Pitfalls
The most pervasive pitfall in post-trauma care is the deep fragmentation of medical disciplines. Neurologists frequently focus exclusively on motor reflexes, spasticity, and cognitive testing while completely ignoring urological health or systemic metabolism, leading to fatal systemic failures like severe pyelonephritis. The Neuro-Visceral Monitoring Matrix directly mitigates this risk by enforcing cross-disciplinary communication and concurrent testing schedules across all physiological systems, ensuring the bladder and kidneys are treated with the same urgency as the spinal cord.
A second major pitfall involves misinterpreting the profound, crushing lethargy of severe neuroendocrine fatigue as simple clinical depression. Without conducting the specific pituitary hormone panels mandated by the monitoring schedule, patients are erroneously placed on psychiatric medications (SSRIs) while their underlying physical hormonal collapse rapidly worsens, leading to severe central weight gain and osteoporosis. The Matrix prevents this by requiring baseline and recurring biochemical endocrine screening. Clinical studies show misdiagnosis of endocrine failure frequently occurs in chronic TBI patients.
Finally, relying solely on qualitative physical exams while entirely neglecting objective biomarker trends allows insidious, chronic neurodegeneration to progress completely unchecked. Integrating GFAP, UCH-L1, and NfL tracking ensures practitioners catch invisible cellular destruction and ongoing axonal shearing before gross, visible functional loss becomes permanent and irreversible.
When to Seek Specialized Expert Help
Baseline monitoring by a general practitioner or general physical rehabilitation specialist is often entirely insufficient for managing severe, evolving neuro-complications. The sudden onset of new, delayed seizures months or years after a brain injury requires immediate referral to a specialized epileptologist. Post-traumatic epilepsy is notoriously difficult to control with standard monotherapy, demanding advanced pharmacokinetic management to prevent life-threatening status epilepticus while minimizing the severe cognitive blunting side effects from the medications themselves.
Furthermore, consideration of any regenerative, exosome, or stem cell therapies requires intense, independent verification by a board-certified neurologist entirely unaffiliated with the treatment clinic. Medical tourism for unverified, unregulated stem cell treatments poses immense physiological and financial risks to vulnerable neurotrauma patients, including the severe danger of introducing central nervous system infections (meningitis), immune rejection, or aberrant, tumor-like cell growth in the spinal canal. Empowering patients to demand comprehensive, multi-specialty evaluations ensures they receive safe, evidence-backed care rather than falling victim to aggressive, scientifically unsubstantiated marketing claims promising impossible cures.
Frequently Asked Questions
How is a motor nervous system examination performed?
A motor nervous system examination is performed systematically by testing specific muscle groups (myotomes) against active resistance to grade strength from 0 to 5. Clinicians begin at the cervical levels (testing arm flexion) and proceed downward to the sacral levels (testing toe movement). This quantitative approach allows for the precise identification of the Neurological Level of Injury. For instance, testing wrist extensors isolates the C6 nerve root function. Results may vary depending on patient consciousness and acute pain limitations.
What is involved in quantitative neuromuscular monitoring?
Quantitative neuromuscular monitoring involves using objective technological instruments, such as acceleromyography (AMG) or electromyography (EMG), to measure the exact electrical response of a muscle to nerve stimulation. Unlike visual assessments, this technology provides a precise percentage of nerve conduction block. It is routinely used in neuro-ICUs to titrate paralytic medications for patients with severe brain injuries. For example, maintaining a specific train-of-four ratio prevents dangerous spikes in intracranial pressure. Clinicians must ensure equipment calibration for accurate data tracking.
What are the functional sequelae after head trauma?
Functional sequelae after head trauma are the resulting lifestyle and behavioral limitations caused by the underlying physical brain injury. These include the inability to maintain employment, profound memory deficits hindering independent living, and personality changes that strain family relationships. Data shows that cognitive fatigue is the most common functional deficit disrupting daily activities post-TBI. For example, a patient may possess full motor strength but lack the executive function to cook a meal safely. Lifelong occupational therapy is frequently required.
Can the central nervous system regenerate?
The adult central nervous system cannot naturally regenerate severed axons due to the formation of an inhibitory glial scar and a lack of intrinsic growth factors. However, the brain can rewire its surviving neural pathways through a process known as neuroplasticity. Experimental treatments utilizing stem cells and neurotrophins are currently being researched to break down these biological barriers. For instance, intensive functional training forces intact adjacent neurons to adopt lost motor functions. Patients should consult a neurologist regarding clinical trial eligibility.
Conclusion
For clinicians managing severe neurotrauma, protection of the central nervous system requires moving beyond acute stabilization to intercept delayed metabolic and endocrine failures. Routine screening of pituitary hormones is heavily recommended for long-term monitoring, as these delayed failures are highly prevalent post-trauma (PubMed Central, 2026). The best approach combines quantitative ASIA exams, continuous biomarker tracking, and coordinated systemic surveillance.
By implementing The Neuro-Visceral Monitoring Matrix, healthcare providers can dismantle the organ-siloed approach that traditionally leaves CNS injury survivors vulnerable to fatal secondary complications. This cohesive framework specifically targets the insidious metabolic, urological, and hormonal collapse discussed throughout this guide. It ensures that every facet of the patient’s systemic health is continuously evaluated and proactively protected, addressing the root causes of secondary decline outlined in the introduction.
Patients and clinical teams must transition immediately from reactive crisis management to structured, lifelong surveillance protocols. We strongly recommend scheduling a comprehensive multidisciplinary evaluation—including baseline pituitary panels, urological assessments, and advanced neuro-imaging—within the first three to six months post-discharge to establish an accurate chronic care trajectory.
**