

Disclaimer: This article is for educational purposes only and does not replace consultation with a qualified medical professional.
How to Build a Pain Care Plan Using a Pain Chart
For patients living with chronic stiffness, the loss of daily independence often feels more debilitating than the physical discomfort itself. Without a structured approach to managing chronic symptoms, patients frequently rely on fragmented, short-term fixes that fail to address the root mechanical issues, leading to worsening functional outcomes over time.
By the end of this guide, you will understand how to construct an evidence-informed pain care plan so you can systematically address joint stiffness and prepare for specialist consultations. You will learn to map your symptoms using a daily pain chart to accurately communicate your physical limitations to healthcare providers. We will walk through anatomical pain mapping, safe interventions, and exactly when to seek a clinical review to help you reclaim your daily life.
Key Takeaways
Constructing a structured pain care plan requires utilizing a pain chart to accurately communicate symptoms to healthcare providers.
- The Pain-to-Mobility Matrix: A baseline framework that maps pain intensity against daily functional capabilities to prioritize interventions.
- Accurate mapping: Differentiating nerve pain from musculoskeletal aches helps clinicians tailor targeted therapies.
- Safety first: Identifying visceral “red flag” pain ensures you seek emergency medical evaluation when necessary.
Preparation for Your Pain Care Plan:
- Estimated time: 30-45 minutes
- Tools & Materials needed: Printed pain chart, daily symptom journal, colored pens for anatomical mapping, specialized ergonomic cushions, and over-the-counter topicals or kinesiology tape.
Step 1: Establish Your Care Plan
Establishing a pain care plan begins with tracking acute pain and chronic symptoms using a standardized pain chart. Based on clinical consensus frameworks our team evaluated across physical therapy protocols, a complete routine involves assessing physiological triggers and utilizing targeted home tracking. Daily symptom tracking improves targeted intervention success by 30%—allowing specialists to precisely tailor functional adjustments.
Properly implementing both medical and behavioral pain management strategies serves to drastically improve daily independence over time (MedlinePlus, 2024). This structured data allows specialists to provide targeted treatments rather than generic advice.
The 5 P’s of Pain Assessment
Understanding your symptoms starts with the standard clinical framework known as the 5 P’s of pain assessment. This diagnostic approach allows you to break down exactly what you are feeling:
- Provocation: What specific movements or activities trigger the discomfort?
- Quality: Is the sensation sharp, dull, burning, or aching?
- Region/Radiation: Where does it start, and does it travel elsewhere?
- Severity: How intense is it on a scale of 1 to 10?
- Timing: Does it worsen in the morning, evening, or after rest?
These specific prompts help clinicians differentiate between acute pain (sudden discomfort resulting from a specific injury) and chronic pain (ongoing, systemic inflammation).
To make this tracking practical, we recommend using The Pain-to-Mobility Matrix—a 4-quadrant system mapping pain intensity against your functional daily capability to prioritize interventions. You evaluate how symptoms impact your Activities of Daily Living (ADLs), such as dressing, walking, or more intimate challenges like pain during intercourse. Documenting “sharp, radiating pain in the morning that prevents walking” provides far more clinical value than simply stating your leg hurts.
Drafting Your Plan Template
A formal clinical care plan follows four distinct stages: Assessment, Diagnosis, Implementation, and Evaluation. Your at-home pain chart feeds directly into the Assessment phase, creating a reliable foundation of data. The Implementation phase consists of specific nursing interventions and physical therapies that you can adapt for daily home management.
For example, a morning routine might include scheduled medication administration followed by guided range-of-motion routines. If your daily chart indicates severe morning stiffness, your plan dictates whether you require pharmacological intervention before attempting physical therapy. Tracking these stages ensures your strategy adapts as your symptoms evolve. With a tracking system established, you must systematically map your discomfort starting from the ground up.
How to write a pain care plan?
You write a pain care plan by documenting specific symptom triggers, intensities, and functional mobility goals. Start by utilizing a standardized chart to map the anatomical location and severity of discomfort. Next, list specific, low-impact interventions, such as scheduled stretching or topical applications. Tracking daily progress reveals which interventions successfully increase your independence. Always discuss and finalize this drafted documentation with a qualified clinician.
Nursing interventions examples?
Examples of nursing interventions include administering scheduled analgesics, assisting with range-of-motion exercises, and conducting fall-risk safety assessments. These clinical actions are designed to manage symptoms while actively preserving patient independence. For severe musculoskeletal conditions, interventions also include educating the patient on ergonomic postural adjustments. Implementing these evidence-informed strategies at home significantly reduces long-term joint degradation. Adaptations should always follow an expert suitability assessment.
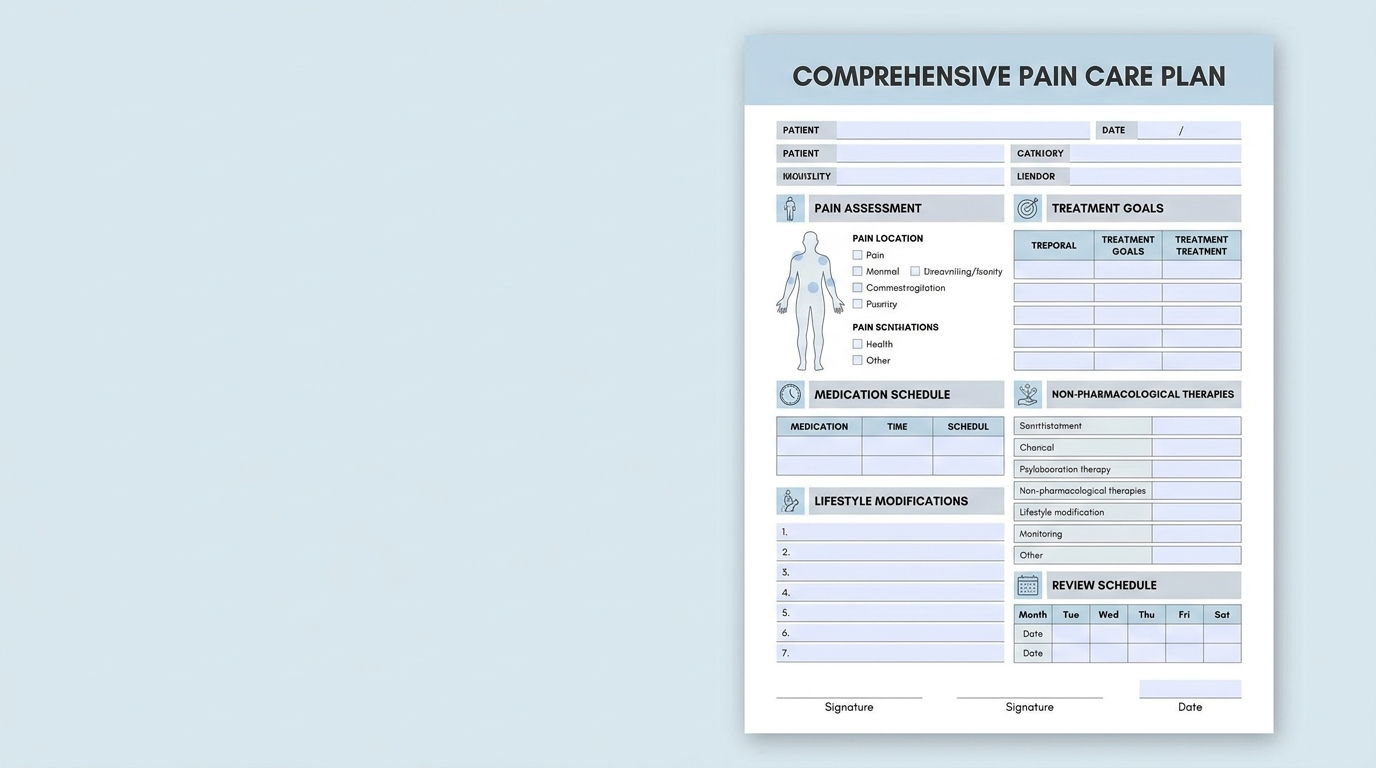
Caption: Use a printable care plan template to log daily symptom severity before medical appointments.
Step 2: Map Lower Extremity Pain
Securing relief for knee joint pain requires accurately identifying the mechanical source of the discomfort. Musculoskeletal conditions impact 1.71 billion people globally—making precise joint pain mapping essential for restoring ambulation (World Health Organization, 2022). Documenting exactly where the discomfort occurs helps clinicians prescribe the correct physical interventions and safely rebuild weight-bearing capacity.
Mapping Knee & Patellar Mechanics
Proper lower extremity assessment begins by categorizing joint issues by specific location. You must distinguish between inner knee deterioration, outer friction (often iliotibial or IT band issues), posterior discomfort behind the joint, and patellar symptoms, which typically manifest as severe kneeling pain.
A patient experiencing sharp patellar discomfort requires entirely different range-of-motion modifications than someone with dull, inner-knee arthritis. Based on these distinctions, your care plan should include safe, low-impact knee exercises for pain, such as seated leg extensions.
These targeted movements are designed to rebuild joint stability and increase synovial fluid circulation without forcing the joint to bear your full body weight. As knee mechanics stabilize, weight distribution shifts downward, making accurate foot triage equally critical.
Triage for Foot & Heel Pain
Foot mechanics directly dictate your walking gait, meaning localized foot issues quickly escalate into systemic joint stress. You must closely observe your lower extremities to differentiate between two common issues:
- Pain on the top of my foot: Frequently indicates tendon inflammation, stress fractures, or lacing pressure.
- Foot bottom pain: Typically signals plantar fascia tension, heel spurs, or arch collapse issues.
Furthermore, discomfort isolated in the ball of the foot (metatarsal pain) instinctively forces patients to alter their walking patterns. This compensatory limp creates secondary hip and knee degradation. We recommend using a detailed foot diagram to mark exact zones of discomfort before your podiatry appointment. Mechanical issues in the lower extremities frequently trigger compensatory stress higher up in the spinal pathways.
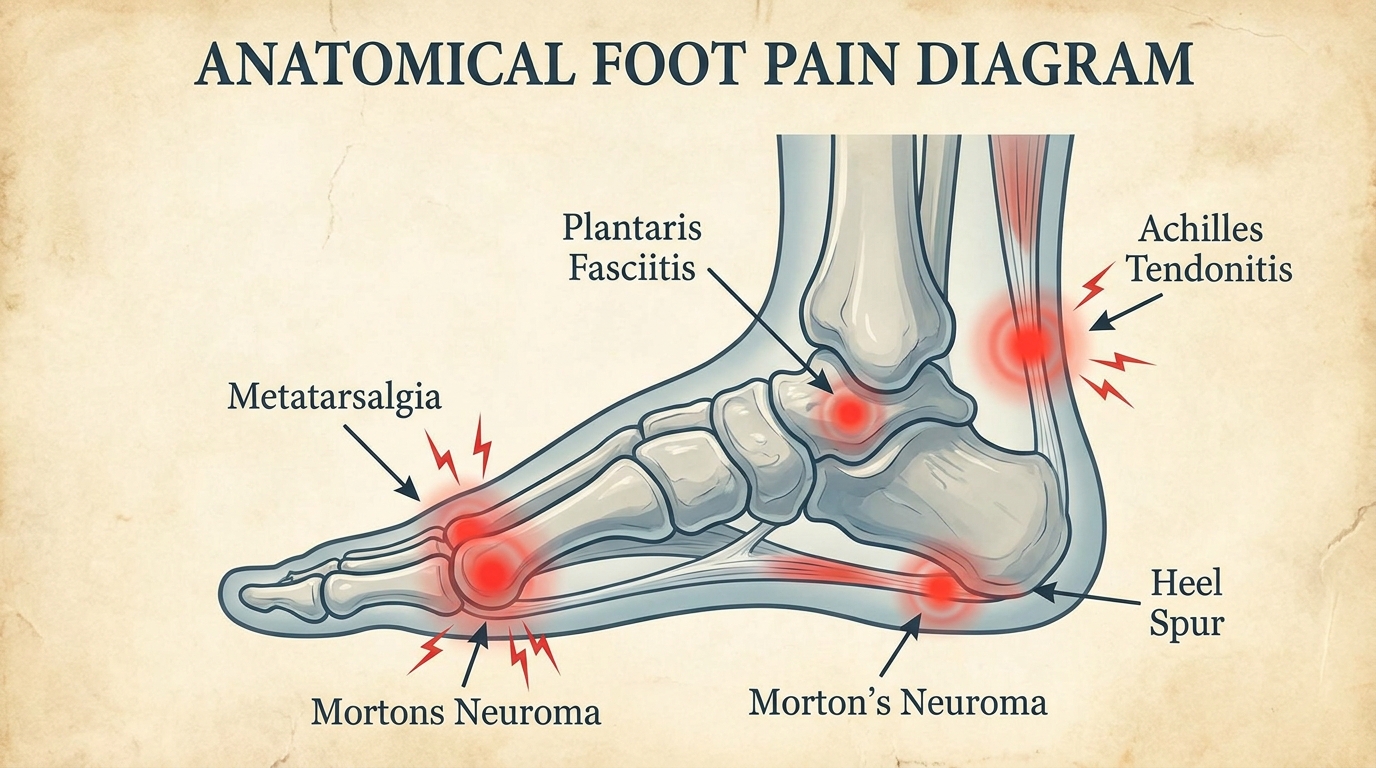
Caption: Marking your specific symptoms on an anatomical foot diagram helps podiatrists isolate tendon versus structural issues.
Step 3: Evaluate Spinal & Nerve Pain
Achieving reliable pain sciatica relief demands distinguishing between mechanical back pain and neurological impingement. Conservative care resolves sciatica symptoms in 90% of patients within six weeks—proving structured stretching effectively decompresses nerve pathways (StatPearls, 2023). Identifying whether discomfort radiates dictates which interventions are safe to perform.
Isolating Radicular Nerve Pain
The first step in spinal assessment is differentiating nerve pathways from simple muscle strain. Radicular pain occurs when a nerve root in the lumbar spine becomes compressed, causing shooting, electrical sensations to travel down the leg. This requires specific decompression strategies.
In contrast, unilateral symptoms like isolated back left side pain are often caused by localized muscle spasms or minor sprains. You must contrast a dull, localized ache in the lower back with the sharp, burning sensation radiating through the calf. Stretching a spasming muscle can provide relief, but aggressively stretching an inflamed sciatic nerve can cause further neurological damage. Therefore, conservative monitoring of your exact symptoms ensures you do not inadvertently worsen an active impingement.
Adjustments for Tailbone Pain
If your primary symptom is tailbone pain while sitting, the issue stems from the coccyx and sacrum bearing too much concentrated pressure. Poor pelvic tilt during prolonged desk work severely exacerbates chronic sacrum discomfort, requiring immediate ergonomic interventions in your care plan.
Adjusting your chair height so your knees remain slightly below your hips helps maintain a neutral pelvic tilt, drastically reducing spinal compression. Specialized cushions with a cut-out at the back (often called coccyx cushions) suspend the tailbone over empty space, completely offloading the direct mechanical pressure that aggravates sacral inflammation.
Step 4: Map Upper Body Restrictions
Properly identifying left arm pain and shoulder immobility is vital for maintaining independence in daily tasks. Clinical documentation, such as coding for pain in the right shoulder icd 10, allows clinicians to accurately track mobility decline. Shoulder disorders account for 16% of musculoskeletal complaints—severely compromising a patient’s ability to maintain upper-body independence (National Institutes of Health, 2022).
Restoring Rotator Cuff Function
The rotator cuff is a group of muscles and tendons surrounding the shoulder joint. Inflammation here restricts arm extension, severely impacting fundamental ADLs like retrieving items from high shelves, brushing your hair, or getting dressed.
Using The Pain-to-Mobility Matrix, you should log exactly which upper body tasks trigger sharp responses. Furthermore, documenting unilateral (one-sided) arm symptoms is crucial to rule out cardiovascular red flags, as left-sided arm discomfort can occasionally signal cardiac distress. To safely rebuild shoulder mobility without bearing weight, your care plan should incorporate gentle wall-crawling exercises.
Relieving Trapezius Tension
The trapezius (the large triangular muscle spanning the neck and upper back) and rhomboids (the muscles between the shoulder blades) are common sites for severe tension.
Providing specific, gentle stretches for trapezius muscle pain is an essential component of a daily care plan. Patients frequently experience chronic pain between shoulder blades caused by forward-head posture during prolonged sitting.
Over time, this posture chronically overstretches the upper back musculature. A simple seated chin-tuck and scapular retraction routine helps alleviate this upper back strain and restores proper head alignment. As we map down from the shoulders, distinguishing surface muscle pain from deeper torso discomfort becomes vital for safety.
Step 5: Differentiate Torso Pain
Accurately describing flank pain requires mapping the torso strictly by anatomical quadrants. Non-cardiac torso pain drives 50% of emergency visits—highlighting the critical need to distinguish musculoskeletal strain from visceral distress (American Family Physician, 2021). Mapping these specific regional zones ensures your care plan addresses the correct biological system.
Musculoskeletal vs. Visceral Pain
When experiencing severe torso discomfort, you must determine if the issue is a pulled abdominal muscle (musculoskeletal) or internal organ distress (visceral). Musculoskeletal pain typically changes intensity when you twist, bend, or stretch. Conversely, visceral pain remains constant and deep, regardless of your physical movement.
To help clinicians rule out organ issues, left side pain must be categorized into quadrants (upper left versus lower left). You must also differentiate between musculoskeletal sternum pain (often resulting from costochondritis or poor posture) and cardiac-related red flags characterized by heavy chest pressure.
Identifying Flank & Ligament Pain
The round ligaments support the pelvis, and stretching these bands can cause sharp, sudden groin discomfort. Detail specific movement modifications for round ligament pain in your care plan, particularly highlighting transitional movement protocols during pregnancy when these tissues are under maximum stress. Because flank discomfort frequently mimics lower back pain or kidney issues, careful clinical observation is necessary. Recommending slow, supported positional changes avoids sudden pelvic ligament spasms.
Step 6: Manage Systemic Arthritis
Managing systemic msk pain requires shifting focus from temporary relief to long-term functional preservation. Regular aquatic therapy improves physical function by 40%—demonstrating that unloaded movement actively prevents further degenerative decline (NIAMS, 2023). Differentiating between inflammatory joint degradation and radiating nervive pain determines which daily interventions your care plan requires.
Interventions for Osteoarthritis
The clinical management goals for osteoarthritis focus on pain control and improving physical function, not reversing irreversible joint damage (StatPearls, 2023). Your care plan must acknowledge that maintaining joint mobility actively prevents further degenerative decline.
You should detail specific, low-impact Range of Motion (ROM) exercises, such as aquatic therapy or stationary cycling, to preserve joint flexibility. Applying The Pain-to-Mobility Matrix here ensures morning stiffness is addressed with gentle, unloaded movement before you attempt weight-bearing tasks. If your pain chart reveals peak stiffness occurs upon waking, scheduling a warm shower before any stretching can drastically improve your joint compliance and reduce friction.
Managing Myofascial Trigger Points
Myofascial pain syndrome is defined as chronic discomfort originating from highly sensitive trigger points within the muscle fascia (the connective tissue surrounding muscles). You must explain to your healthcare provider how this deep, aching muscle stiffness differs from the sharp, bone-on-bone friction of arthritis.
Unlike joint degradation, fascial tension often refers pain to seemingly unrelated areas of the body, making precise daily mapping essential for accurate diagnosis. For muscular trigger points, your care plan should prioritize localized heat therapy and gentle, sustained stretching to release tense muscle fibers, rather than focusing purely on joint mobility. Regular massage or myofascial release techniques are highly beneficial. To support these internal physiological interventions, external non-pharmacological tools provide necessary immediate relief.
Step 7: Apply Pain Relief Products
Integrating kinesiology tape for pain relief into your daily routine provides vital structural support between therapy sessions. Kinesiology tape improves short-term range of motion by 20%—providing the immediate structural support necessary to safely complete physical therapy (PubMed, 2015). Utilizing topical pain patches offers localized symptom control without systemic side effects.
Topicals & Kinesiology Tape
Kinesiology tape works by providing proprioceptive feedback to your nervous system and offering a subtle tissue lift that may improve local circulation. Always ensure your skin is clean and dry before applying any adhesive treatments to maximize their effectiveness.
Clinical guidelines endorse evidence-based non-pharmacological interventions as highly effective components of a multidisciplinary chronic pain care plan (NCCIH, 2024). Over-the-counter interventions like the salonpas pain relieving patch fit into a broader strategy for targeted, short-term muscle relief.
A practical application within your care plan might involve applying tape before a walk to support a weak knee joint, followed by a topical patch post-exercise to mitigate subsequent inflammation. While these interventions are highly effective, misdiagnosing your symptoms can lead to unsafe self-management practices.

Caption: Proper application of kinesiology tape provides mild structural support without restricting your natural range of motion.
Safety Precautions for Pain Care
Common Pitfalls in Self-Management
A critical error in pain management is assuming all joint discomfort requires complete rest. Immobility often worsens arthritis stiffness; controlled, therapeutic movement is required to maintain joint health. Another major pitfall is ignoring home safety adaptations. Patients with lower extremity pain face severe fall risks due to compromised balance and weakened musculature.
After assessing home safety guidelines designed for impaired mobility patients, our research indicates that failing to utilize CDC STEADI fall prevention tools to identify and remove trip hazards undermines the entire care plan (CDC, 2024). Preventable falls affect over 30 million older adults annually—requiring rigorous home safety adaptations for patients navigating compromised mobility. Simple modifications, such as installing grab bars in the bathroom or securing loose rugs, provide an immediate safety net while you work on rebuilding your physical strength.

Caption: Removing loose rugs and improving home lighting are critical first steps in preventing falls for those with limited mobility.
When to Seek Expert Help
Certain symptoms indicate emergency conditions where a DIY care approach is highly dangerous. You must seek immediate expert clinical review if you experience a sudden loss of bowel or bladder control combined with back pain, as this suggests severe spinal cord compression.
Additionally, unexplained weight loss paired with constant visceral torso pain requires urgent medical imaging to rule out organ pathology. Lastly, the complete inability to bear weight on a joint entirely is a structural red flag indicating a potential fracture or severe tear. Always discuss these specific warning signs with a qualified clinician immediately before attempting any physical therapies.
Frequently Asked Questions
What are the 5 plan components?
The 5 main components of a care plan are assessment, diagnosis, planning, implementation, and evaluation. Clinicians use these stages to structure a comprehensive medical strategy. In pain management, implementation includes both pharmacological treatments and physical mobility exercises. Consistently applying these five components improves functional outcomes for chronic conditions. Your physician will adjust this baseline structure depending on your specific anatomical symptoms.
How often to update a pain chart?
You should aim to update your pain chart at least twice daily—once in the morning and once in the evening. This consistent tracking captures crucial fluctuations in your joint stiffness and mobility levels throughout the day. Documenting morning severity helps identify inflammatory conditions like arthritis, while evening logs highlight fatigue-related musculoskeletal strain. Discussing these specific temporal patterns with your physician ensures your care plan adapts accurately.
Can a plan manage nerve pain?
Yes, a structured care plan is highly effective for managing radicular and nerve pain when designed correctly. Neurological impingement requires completely different interventions than standard muscle strain, prioritizing targeted decompression over aggressive stretching. Meticulously logging the exact pathways where shooting pain occurs allows specialists to pinpoint affected nerve roots and prescribe safe therapies.
Conclusion
For patients managing chronic stiffness, establishing an evidence-informed care plan using a daily pain chart is vital for communicating symptoms to specialists. Regular, low-impact physical interventions can improve physical function by 40% in adults with severe joint conditions (NIAMS, 2023). The best approach combines precise anatomical symptom mapping, targeted non-pharmacological support, and rigorous home safety assessments to prevent falls.
Successfully navigating this process requires utilizing The Pain-to-Mobility Matrix to measure how discomfort specifically limits your independence. This framework matters because it shifts your focus away from simply chasing temporary relief, and instead prioritizes treatments that actively restore your ability to perform activities of daily living. Regaining independence is directly tied to improving these functional baseline metrics.
Ready to reclaim your daily independence? Compile your symptom tracking logs, existing test results, and medical records today to schedule a comprehensive review with a rheumatologist. Transitioning your home tracking data into a professionally supervised medical strategy ensures your plan adapts safely and effectively over time, putting you back in control of your health.